Uploaded November 2020 | Updated September 2026, 5 hours ago
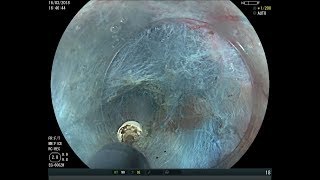
The first case is about an 80-year-old patient with a Paris IIa and IIb lesion of the incisura creeping towards the pylorus, the anterior and posterior wall of the antrum. The borders of the lesion are were not clearly visible. Therefore, we decided to proceed to broad resection of the incisura and antrum. After marking the lesion, the dissection begun from the most difficult part, which was the internal part of the pylorus. Then we continued with the rest of the lesion. Dissection was mainly performed with a ball type knife, and in some areas with IT Knife nano. Clip and band countertraction was used to accelerate the procedure. The lesion was lifted with a mixture of hydroxyethyl starch, indigocarmine and adrenaline. At this segment of the procedure we watch the dissection of the anterior gastric wall. With the help of gravity and countertraction the dissection is fast and safe. After resection of 80% of the lesion, we decided to change the axis of countertraction by removing the clip that holded the specimen. With the help of a new clip, the specimen was re-attached in a different position. The modification of countertraction improved the dissection plane and the procedure was completed successfully in just two hours. The patient was hospitalized for 1 night and had an uneventful recovery. Histology showed, multifocal high and low grade dysplasia with negative margins. Therefore, the patient spared the need for partial gastrectomy.
The second case is about a 60-year-old patient with extensive enteric metaplasia. The patient underwent narrow band examination with multiple biopsies. Histology showed low grade dysplasia at the area of the incisura. The patient underwent clip and band ESD, with wide field resection of the lesser curvature including the incisura and part of the antrum. The procedure lasted 3 hours. The patient was hospitalized for 24 hours and had an uneventful recovery. Examination of the specimen disclosed multifocal low-grade dysplasia.
These two cases illustrate the feasibility of wide-field whole-antral and whole-incisura ESD for extensive dysplastic areas. En-bloc resection offers obvious advantages in terms of decreasing recurrence risk, and obviating repeat interventions.
The first case is about an 80-year-old patient with a Paris IIa and IIb lesion of the incisura creeping towards the pylorus, the anterior and posterior wall of the antrum. The borders of the lesion are were not clearly visible. Therefore, we decided to proceed to broad resection of the incisura and antrum. After marking the lesion, the dissection begun from the most difficult part, which was the internal part of the pylorus. Then we continued with the rest of the lesion. Dissection was mainly performed with a ball type knife, and in some areas with IT Knife nano. Clip and band countertraction was used to accelerate the procedure. The lesion was lifted with a mixture of hydroxyethyl starch, indigocarmine and adrenaline. At this segment of the procedure we watch the dissection of the anterior gastric wall. With the help of gravity and countertraction the dissection is fast and safe. After resection of 80% of the lesion, we decided to change the axis of countertraction by removing the clip that holded the specimen. With the help of a new clip, the specimen was re-attached in a different position. The modification of countertraction improved the dissection plane and the procedure was completed successfully in just two hours. The patient was hospitalized for 1 night and had an uneventful recovery. Histology showed, multifocal high and low grade dysplasia with negative margins. Therefore, the patient spared the need for partial gastrectomy.
The second case is about a 60-year-old patient with extensive enteric metaplasia. The patient underwent narrow band examination with multiple biopsies. Histology showed low grade dysplasia at the area of the incisura. The patient underwent clip and band ESD, with wide field resection of the lesser curvature including the incisura and part of the antrum. The procedure lasted 3 hours. The patient was hospitalized for 24 hours and had an uneventful recovery. Examination of the specimen disclosed multifocal low-grade dysplasia.
These two cases illustrate the feasibility of wide-field whole-antral and whole-incisura ESD for extensive dysplastic areas. En-bloc resection offers obvious advantages in terms of decreasing recurrence risk, and obviating repeat interventions.