Uploaded February 2017 | Updated September 2026, 7 hours ago
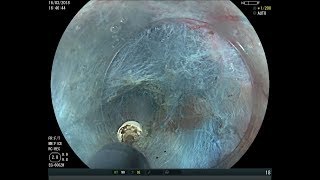
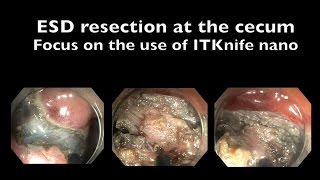
This video demonstrates the resection of gastric a carcinoid tumor with the pocket creation method. The main purpose of this production is to present the management of adverse events that may be encountered during a gastric ESD such as bleeding and small wall defects. The lesion was located at the proximal part of the posterior wall of the stomach. EUS evaluation showed a hypoechoic lesion limited into the mucosa and submucosa. The resection was performed under general anesthesia. We used an Olympus 185 Gastroscope with a soft hood and insufflation of CO2. ESD was initially performed with a tip cutting knife and then with a blunt tip cutting knife. A water pump was connected to the endoscope for flushing. The lesion was lifted with a 23 Gauge needle using a mixture of Voluven and indigocarmine. When necessary adrenaline was injected as needed. For coagulation of larger vessels we used a hot biopsy forceps. After inspection, small markers where placed and the lesion was lifted. An horizontal incision was made at the oral side of the tumor. The plan was to create an horizontal opening in order to create a submucosal tunnel. During the whole procedure we encountered mild and severe bleedings due to rich vascularization of the submucosal layer. Minor bleedings were managed with the tip of the knife using forced coagulation. Larger vessels were coagulated with a hot biopsy forceps using soft coagulation. The submucosal tunnel was progressively expanded both distally and then laterally. For dissection we applied Endocut Q, Effect 3 and in areas with rich vascularization Drycut. Poor visualization during bleedings resulted into suboptimal dissection and to small wall defects. In case of inadvertent perforation the surrounding area has to be dissected prior to clip closure, because otherwise the clip will interfere with further dissection.However, in this particular highlight of the procedure, dissection of the area around the perforation was complicated with a major bleeding. Therefore, we gave priority into aspirating the liquids and to closing the defect with a large clip. Then, we identified the source of bleeding and coagulated the bleeding vessel. An additional tiny perforation was closed with an EZ clip. You may have noticed that we have switched to an IT knife.This is a blunt tip knife that when used appropriately it is safer than tip cutting knives in areas with poorer visualization, with perpendicular access or presence of larger vessels.The decision to change knife in the middle of the procedure accelerated the dissection and solved the problem of difficult access.
At the end of the procedure we inspected the artificial ulcer for wall defects and vessels. All visible vessels were coagulated and multiple clips were placed to closed the artificial ulcer. This later decision is not recommended by Japanese experts however, in our case series of gastric ESDs we have not yet experienced any case of late bleeding or perforation.The patient received oral antibiotics and double dose PPI treatment and was discharged 24 hours later with liquid diet and had an uneventful recovery. Histology disclosed a R0 resection of a well differentiated carcinoid.
This video demonstrates the resection of gastric a carcinoid tumor with the pocket creation method. The main purpose of this production is to present the management of adverse events that may be encountered during a gastric ESD such as bleeding and small wall defects. The lesion was located at the proximal part of the posterior wall of the stomach. EUS evaluation showed a hypoechoic lesion limited into the mucosa and submucosa. The resection was performed under general anesthesia. We used an Olympus 185 Gastroscope with a soft hood and insufflation of CO2. ESD was initially performed with a tip cutting knife and then with a blunt tip cutting knife. A water pump was connected to the endoscope for flushing. The lesion was lifted with a 23 Gauge needle using a mixture of Voluven and indigocarmine. When necessary adrenaline was injected as needed. For coagulation of larger vessels we used a hot biopsy forceps. After inspection, small markers where placed and the lesion was lifted. An horizontal incision was made at the oral side of the tumor. The plan was to create an horizontal opening in order to create a submucosal tunnel. During the whole procedure we encountered mild and severe bleedings due to rich vascularization of the submucosal layer. Minor bleedings were managed with the tip of the knife using forced coagulation. Larger vessels were coagulated with a hot biopsy forceps using soft coagulation. The submucosal tunnel was progressively expanded both distally and then laterally. For dissection we applied Endocut Q, Effect 3 and in areas with rich vascularization Drycut. Poor visualization during bleedings resulted into suboptimal dissection and to small wall defects. In case of inadvertent perforation the surrounding area has to be dissected prior to clip closure, because otherwise the clip will interfere with further dissection.However, in this particular highlight of the procedure, dissection of the area around the perforation was complicated with a major bleeding. Therefore, we gave priority into aspirating the liquids and to closing the defect with a large clip. Then, we identified the source of bleeding and coagulated the bleeding vessel. An additional tiny perforation was closed with an EZ clip. You may have noticed that we have switched to an IT knife.This is a blunt tip knife that when used appropriately it is safer than tip cutting knives in areas with poorer visualization, with perpendicular access or presence of larger vessels.The decision to change knife in the middle of the procedure accelerated the dissection and solved the problem of difficult access.
At the end of the procedure we inspected the artificial ulcer for wall defects and vessels. All visible vessels were coagulated and multiple clips were placed to closed the artificial ulcer. This later decision is not recommended by Japanese experts however, in our case series of gastric ESDs we have not yet experienced any case of late bleeding or perforation.The patient received oral antibiotics and double dose PPI treatment and was discharged 24 hours later with liquid diet and had an uneventful recovery. Histology disclosed a R0 resection of a well differentiated carcinoid.