Uploaded January 2025 | Updated September 2026, 1 day ago
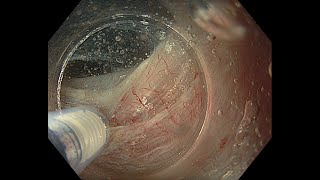
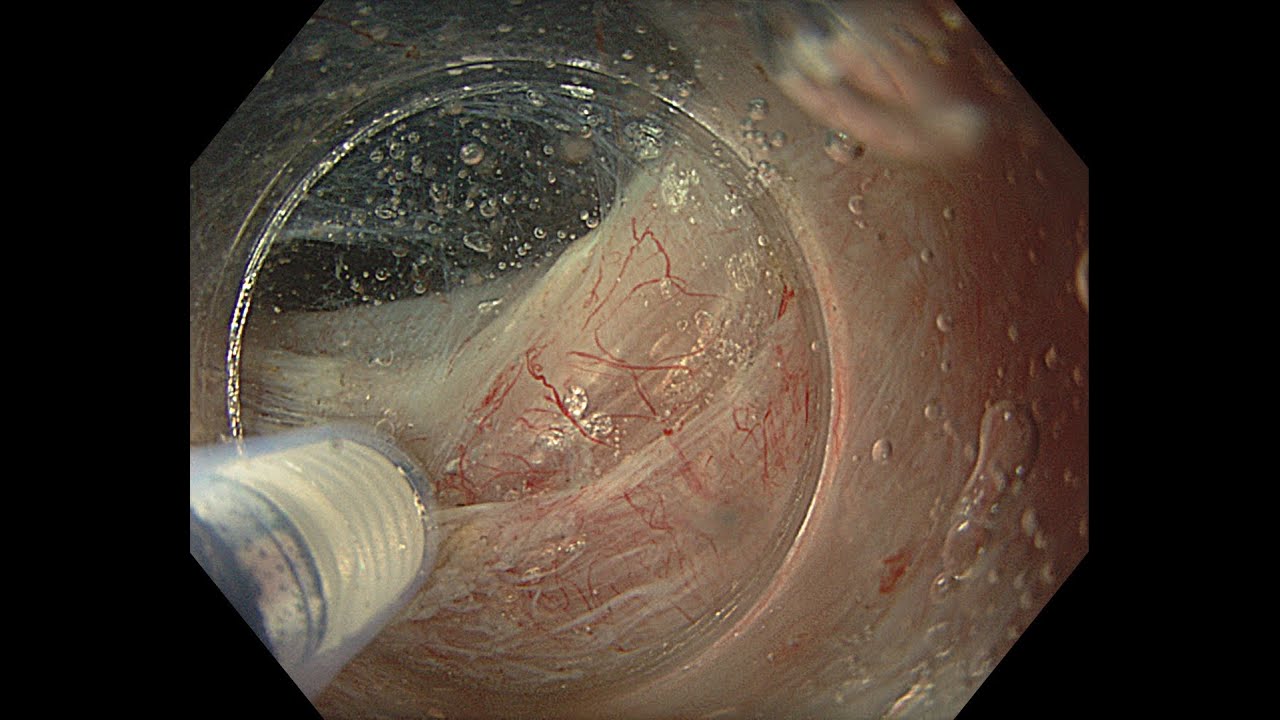
Underwater peroral endoscopic myotomy was initially presented as an alternative approach for the treatment of achalasia with only few case reports published since its initial description. The theoretical advantage of using saline infusion instead of CO2 is the diminished risk of gas related events such as capnoperitoneum, tension pneumothorax or pneumomediastinum. However, in our experience the major advantage of working undersaline, is the stabilization of the endoscope in the setting of increased esophageal motility. The purpose of this video is to illustrate the advantages of undersaline peroral endoscopic tunneling combined with partial myotomy in the setting of hypercotractile esophagus. In this rare disorder the increased motility of the esophagus makes the procedure challenging and raises the risk of inadvertent mucosal damage. However, by performing undersaline dissection the mucosa floats away from the muscle layer and the spasms of the esophagus do not interfere with the dissection plane. In addition, by performing partial myotomy during tunneling the axis of the tunnel is straightened and the intensity of contractions is significantly diminished. When both techniques are applied the procedure becomes safer and faster. Once the tunnel is completed the saline is aspirated in order to diminish the risk of postoperative pleural effusions and standard myotomy is performed. In conclusion, we believe that undersaline tunneling combined with partial myotomy is an innovative approach for faster and safer dissection in motility disorders with intense esophageal contractions.
Underwater peroral endoscopic myotomy was initially presented as an alternative approach for the treatment of achalasia with only few case reports published since its initial description. The theoretical advantage of using saline infusion instead of CO2 is the diminished risk of gas related events such as capnoperitoneum, tension pneumothorax or pneumomediastinum. However, in our experience the major advantage of working undersaline, is the stabilization of the endoscope in the setting of increased esophageal motility. The purpose of this video is to illustrate the advantages of undersaline peroral endoscopic tunneling combined with partial myotomy in the setting of hypercotractile esophagus. In this rare disorder the increased motility of the esophagus makes the procedure challenging and raises the risk of inadvertent mucosal damage. However, by performing undersaline dissection the mucosa floats away from the muscle layer and the spasms of the esophagus do not interfere with the dissection plane. In addition, by performing partial myotomy during tunneling the axis of the tunnel is straightened and the intensity of contractions is significantly diminished. When both techniques are applied the procedure becomes safer and faster. Once the tunnel is completed the saline is aspirated in order to diminish the risk of postoperative pleural effusions and standard myotomy is performed. In conclusion, we believe that undersaline tunneling combined with partial myotomy is an innovative approach for faster and safer dissection in motility disorders with intense esophageal contractions.