Uploaded May 2026 | Updated September 2026, 15 hours ago
ENDOSCOPIC SUBMUCOSAL DISSECTION FOR A BLEEDING GASTRIC HAMARTOMATOUS POLYP PROVOKING ANEMIA AND GASTRIC OUTLET OBSTRUCTION IN A 3-YEAR-OLD PATIENT
Background and Aims
Gastric hamartomatous polyps are rare in children and may present with chronic bleeding, anemia, or gastric outlet obstruction. Surgical resection has traditionally been considered in large symptomatic lesions. We present a challenging case of endoscopic submucosal dissection (ESD) for en bloc removal of a large bleeding gastric hamartomatous polyp in a 3-year-old child.
Μethods
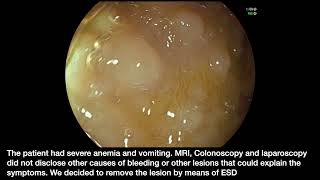
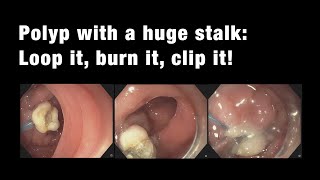
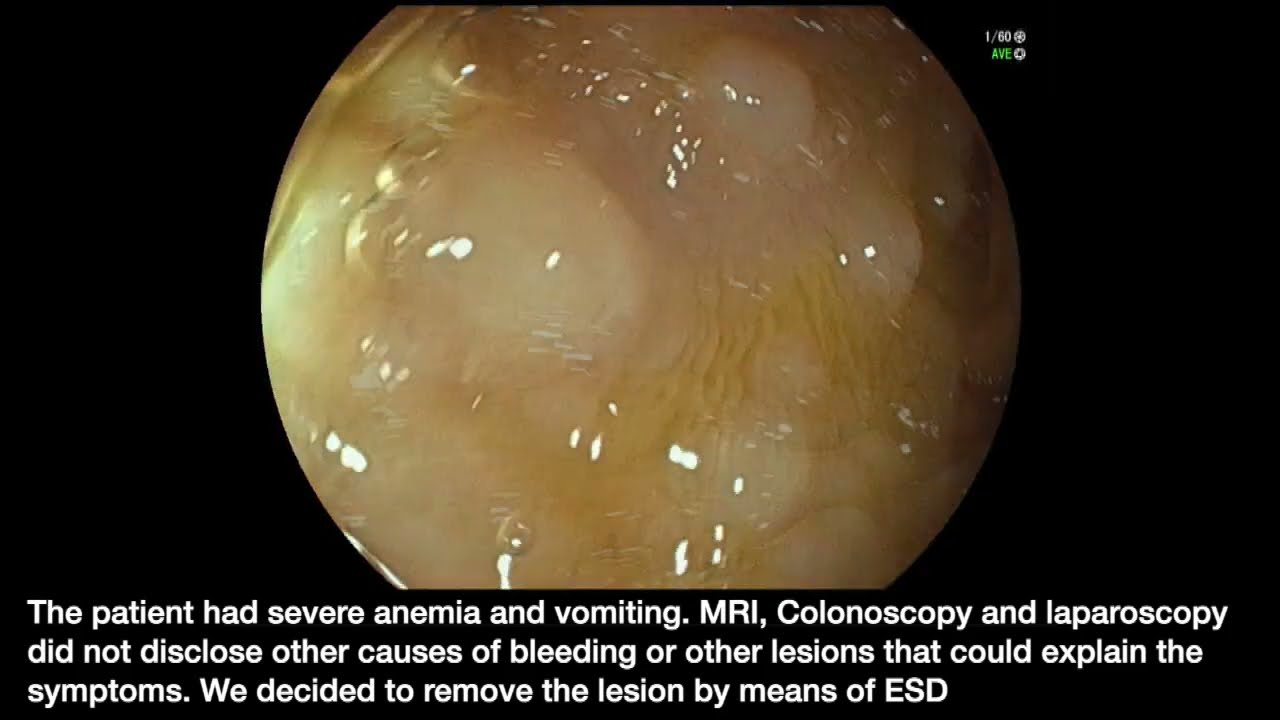
A 3-year-old patient presented with recurrent vomiting, iron-deficiency anemia, melena, and failure to thrive. Upper gastrointestinal endoscopy revealed a large pedunculated hamartomatous polyp arising from the gastric antrum and intermittently prolapsing through the pylorus, causing gastric outlet obstruction. The lesion demonstrated contact bleeding and extensive surface congestion. Endoscopic ultrasound excluded deep mural invasion.
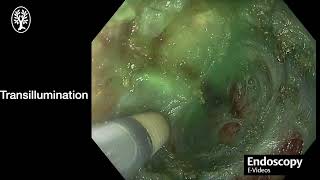
Considering the patient’s age, the symptomatic nature of the lesion, and the desire to avoid surgery, en bloc endoscopic resection was planned. Circumferential mucosal incision and submucosal dissection were performed using an endoscopic knife following submucosal injection. Careful traction and meticulous hemostasis were required due to marked vascularity and limited working space within the pediatric stomach. The lesion was successfully removed en bloc, and the post-ESD defect was partially closed with clips.
Results
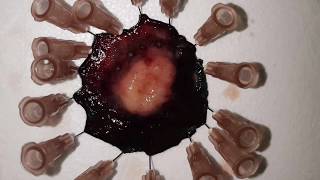
The procedure was completed without intraprocedural or delayed adverse events. Oral feeding was resumed progressively, with complete resolution of vomiting and melena. Hemoglobin levels normalized during follow-up. Histopathological examination confirmed a hamartomatous polyp with negative resection margins. No recurrence was observed during follow-up endoscopy.
Conclusion
ESD may represent a feasible and minimally invasive alternative to surgery for selected large gastric hamartomatous polyps in pediatric patients, even in very young children. Careful case selection and advanced endoscopic expertise are essential to achieve safe en bloc resection in this technically demanding setting.
ENDOSCOPIC SUBMUCOSAL DISSECTION FOR A BLEEDING GASTRIC HAMARTOMATOUS POLYP PROVOKING ANEMIA AND GASTRIC OUTLET OBSTRUCTION IN A 3-YEAR-OLD PATIENT
Background and Aims
Gastric hamartomatous polyps are rare in children and may present with chronic bleeding, anemia, or gastric outlet obstruction. Surgical resection has traditionally been considered in large symptomatic lesions. We present a challenging case of endoscopic submucosal dissection (ESD) for en bloc removal of a large bleeding gastric hamartomatous polyp in a 3-year-old child.
Μethods
A 3-year-old patient presented with recurrent vomiting, iron-deficiency anemia, melena, and failure to thrive. Upper gastrointestinal endoscopy revealed a large pedunculated hamartomatous polyp arising from the gastric antrum and intermittently prolapsing through the pylorus, causing gastric outlet obstruction. The lesion demonstrated contact bleeding and extensive surface congestion. Endoscopic ultrasound excluded deep mural invasion.
Considering the patient’s age, the symptomatic nature of the lesion, and the desire to avoid surgery, en bloc endoscopic resection was planned. Circumferential mucosal incision and submucosal dissection were performed using an endoscopic knife following submucosal injection. Careful traction and meticulous hemostasis were required due to marked vascularity and limited working space within the pediatric stomach. The lesion was successfully removed en bloc, and the post-ESD defect was partially closed with clips.
Results
The procedure was completed without intraprocedural or delayed adverse events. Oral feeding was resumed progressively, with complete resolution of vomiting and melena. Hemoglobin levels normalized during follow-up. Histopathological examination confirmed a hamartomatous polyp with negative resection margins. No recurrence was observed during follow-up endoscopy.
Conclusion
ESD may represent a feasible and minimally invasive alternative to surgery for selected large gastric hamartomatous polyps in pediatric patients, even in very young children. Careful case selection and advanced endoscopic expertise are essential to achieve safe en bloc resection in this technically demanding setting.