Uploaded March 2026 | Updated September 2026, 1 hour ago
Endoscopic reconstruction of complete post-radiation esophageal and neopharyngeal obliteration
A 75-year-old man presented with complete dysphagia due to a 6 cm post-radiation fibrotic obliteration of the cervical esophagus and neopharynx. He had a history of laryngeal carcinoma treated with laryngectomy and chemoradiation therapy seven years earlier, and his nutrition was maintained via a gastrostomy tube.
After multidisciplinary discussion, endoscopic reconstruction of the neopharynx and esophagus was planned. The procedure included: securing the gastrostomy tract with gastropexy, dilating the gastrostomy to accommodate a standard gastroscope, creating a retrograde submucosal tunnel up to the neopharynx, and performing sequential balloon dilations.
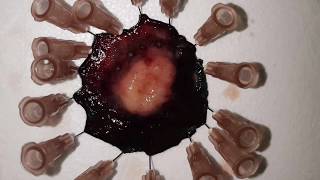
Endoscopic gastropexy was achieved using a double-needle device under endoscopic guidance, introducing a 6 mm endoscope through the gastrostomy. Four sutures were placed to stabilize the tract.
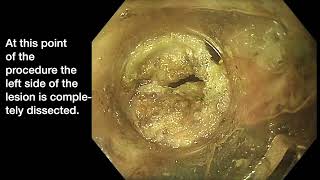
Three weeks later, the gastrostomy site was dilated to 18 mm, allowing retrograde insertion of a 9 mm gastroscope toward the distal end of the atretic segment. A mixture of normal saline and indigo carmine was injected, and fibrotic tissue was dissected using a needle-type knife in Endocut mode, while loose adhesions were treated in spray-coagulation mode.
Step by step, a new lumen was created without fluoroscopic guidance, as the dissection plane was clearly identified endoscopically
by following the axis of the muscle layer.
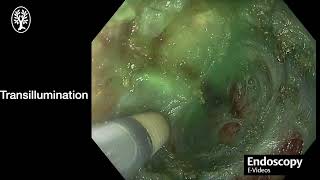
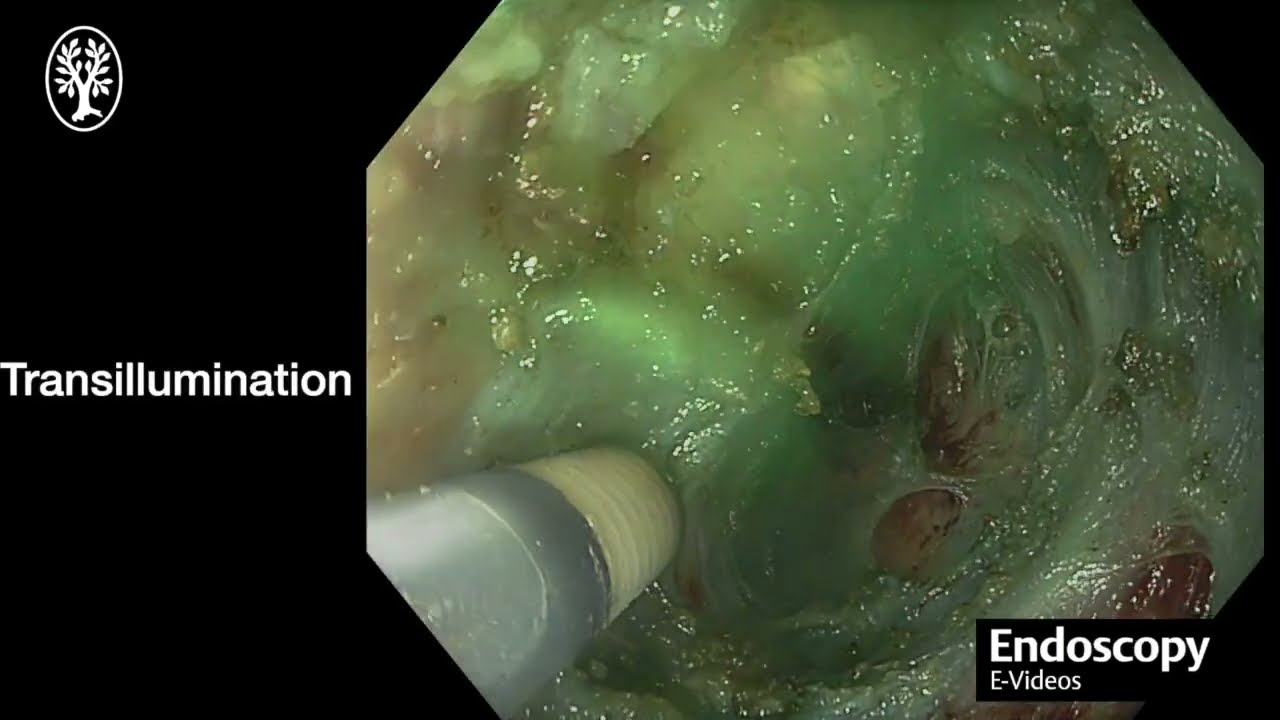
The tunnel was extended proximally to the neopharynx, where transillumination from an orally introduced gastroscope enabled an endoscopic rendezvous. The light of the retrograde endoscope was turned off intermittently to verify alignment of the dissection axis with the antegrade endoscope.
A guidewire was placed to delineate the tunnel and facilitate oral dissection of the proximal component. Reconstruction of the neopharynx was completed via the oral route. For this part of the procedure, a straight cap was attached to the tip of the endoscope to improve access to the dissection plane. The fibrotic tissue of the neopharynx was then carefully dissected using Endocut mode.
and the newly created tract was finally dilated to 15 mm to allow passage of a standard endoscope.
The patient remained NPO, was hospitalized for 48 hours for observation, and was discharged uneventfully without adverse events, apart from transient cervical emphysema and mild neck pain. The nasogastric tube was maintained until the scheduled dilation 14 days later, while the gastropexy sutures were removed one month thereafter. No steroid injection was administered due to its limited efficacy in post-radiation strictures. In addition, the patient declined stent placement because of concerns regarding pain, local discomfort, and the potential risk of fistula formation. The PEG tube was maintained in situ for safety reasons.
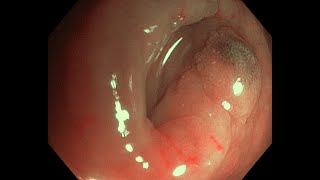
At 9 months of follow up he continues monthly serial balloon dilations up to 15 mm to maintain patency and currently tolerates liquids and soft solids.
Conclusion:
Endoscopic reconstruction of post-radiation esophageal obliteration is feasible but technically demanding. Key factors for a safe and successful outcome include pre-procedural gastropexy to prevent perforation, transillumination guidance for proximal orientation, and long-term sequential dilations to maintain the newly created lumen.
Endoscopic reconstruction of complete post-radiation esophageal and neopharyngeal obliteration
A 75-year-old man presented with complete dysphagia due to a 6 cm post-radiation fibrotic obliteration of the cervical esophagus and neopharynx. He had a history of laryngeal carcinoma treated with laryngectomy and chemoradiation therapy seven years earlier, and his nutrition was maintained via a gastrostomy tube.
After multidisciplinary discussion, endoscopic reconstruction of the neopharynx and esophagus was planned. The procedure included: securing the gastrostomy tract with gastropexy, dilating the gastrostomy to accommodate a standard gastroscope, creating a retrograde submucosal tunnel up to the neopharynx, and performing sequential balloon dilations.
Endoscopic gastropexy was achieved using a double-needle device under endoscopic guidance, introducing a 6 mm endoscope through the gastrostomy. Four sutures were placed to stabilize the tract.
Three weeks later, the gastrostomy site was dilated to 18 mm, allowing retrograde insertion of a 9 mm gastroscope toward the distal end of the atretic segment. A mixture of normal saline and indigo carmine was injected, and fibrotic tissue was dissected using a needle-type knife in Endocut mode, while loose adhesions were treated in spray-coagulation mode.
Step by step, a new lumen was created without fluoroscopic guidance, as the dissection plane was clearly identified endoscopically
by following the axis of the muscle layer.
The tunnel was extended proximally to the neopharynx, where transillumination from an orally introduced gastroscope enabled an endoscopic rendezvous. The light of the retrograde endoscope was turned off intermittently to verify alignment of the dissection axis with the antegrade endoscope.
A guidewire was placed to delineate the tunnel and facilitate oral dissection of the proximal component. Reconstruction of the neopharynx was completed via the oral route. For this part of the procedure, a straight cap was attached to the tip of the endoscope to improve access to the dissection plane. The fibrotic tissue of the neopharynx was then carefully dissected using Endocut mode.
and the newly created tract was finally dilated to 15 mm to allow passage of a standard endoscope.
The patient remained NPO, was hospitalized for 48 hours for observation, and was discharged uneventfully without adverse events, apart from transient cervical emphysema and mild neck pain. The nasogastric tube was maintained until the scheduled dilation 14 days later, while the gastropexy sutures were removed one month thereafter. No steroid injection was administered due to its limited efficacy in post-radiation strictures. In addition, the patient declined stent placement because of concerns regarding pain, local discomfort, and the potential risk of fistula formation. The PEG tube was maintained in situ for safety reasons.
At 9 months of follow up he continues monthly serial balloon dilations up to 15 mm to maintain patency and currently tolerates liquids and soft solids.
Conclusion:
Endoscopic reconstruction of post-radiation esophageal obliteration is feasible but technically demanding. Key factors for a safe and successful outcome include pre-procedural gastropexy to prevent perforation, transillumination guidance for proximal orientation, and long-term sequential dilations to maintain the newly created lumen.