Uploaded March 2026 | Updated September 2026, 8 hours ago
MODIFIED Z-POEM FOR GIANT ZENKER’S DIVERTICULUM USING A TUNNEL-FREE APPROACH, UNDERSALINE IMMERSION AND MUCOSAL TRIMMING
Z-POEM has emerged as an innovative technique with a high success rate for the treatment of Zenker’s diverticulum. Since its introduction, several modifications have been developed, including a mucosal incision directly over the septum, a tunnel-free approach, undersaline dissection, and incision of the mucosal flap at the end of the procedure.
In this video case, we demonstrate the application of these advanced techniques in a complex case of a giant Zenker’s diverticulum.
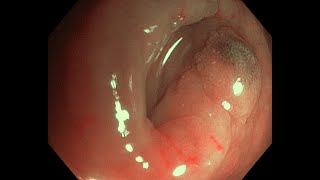
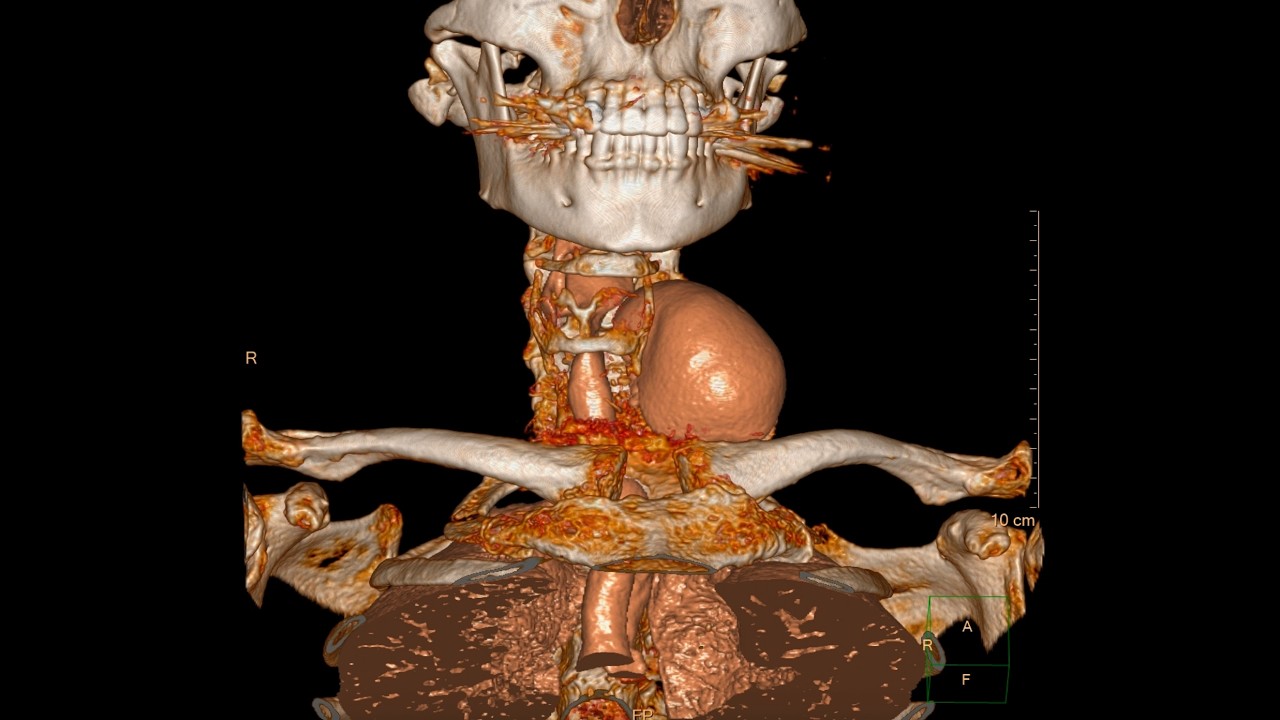
A 59-year-old patient was referred with severe dysphagia due to a giant 9-cm Zenker’s diverticulum. Endoscopy confirmed a large diverticulum associated with a tight upper esophageal stricture. Following multidisciplinary discussion, we proceeded with a modified Z-POEM utilizing the following key techniques:
• Myotomy over the septum for easier access
• Undersaline immersion at the beginning of the procedure to enhance visualization of the submucosal plane
• Tunnel-free approach to allow faster and safer progression
• Extended myotomy across the deepest segment of the cricopharyngeus, both centrally and laterally
• Mucosal flap incision due to the oversized dimensions of the septum
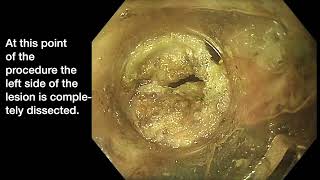
After filling the lumen with normal saline, a mucosal incision was made directly over the septum. Generous submucosal injection was then performed on both sides of the cricopharyngeal muscle, creating submucosal cushions that served as protective barriers during direct myotomy. Because of the limited working space, we continued undersaline immersion and performed dissection in Endocut mode with a needle-type knife.
Once the initial 2 cm of myotomy were completed, the working space widened and we proceeded under CO₂ insufflation. The myotomy was extended to the bottom of the diverticulum and then 2 cm into the esophagus, aiming to reduce recurrence risk. The depth of the myotomy was assessed indirectly by visualizing mucosal discoloration at the diverticulum base.
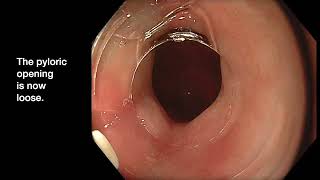
Given the large septal surface, multiple additional incisions were made along the bottom of the septotomy. The oversized mucosal flap was then incised in Endocut mode using a long L-shaped knife, with efforts to maintain symmetrical trimming on both sides.
Closure was achieved with multiple hemostatic clips. The patient remained NPO and underwent a next-day esophagram showing no leak and no contrast retention.
Recovery was uneventful, and at 6-month follow-up, she is completely asymptomatic, tolerating a full diet.
In conclusion, we demonstrate a modified Z-POEM technique tailored for large Zenker’s diverticula, incorporating:
• undersaline immersion to facilitate early dissection
• a tunnel-free approach for efficient septal division
• deep esophageal extension of the myotomy to prevent recurrence, and
• mucosal flap incision to avoid postoperative food retention
MODIFIED Z-POEM FOR GIANT ZENKER’S DIVERTICULUM USING A TUNNEL-FREE APPROACH, UNDERSALINE IMMERSION AND MUCOSAL TRIMMING
Z-POEM has emerged as an innovative technique with a high success rate for the treatment of Zenker’s diverticulum. Since its introduction, several modifications have been developed, including a mucosal incision directly over the septum, a tunnel-free approach, undersaline dissection, and incision of the mucosal flap at the end of the procedure.
In this video case, we demonstrate the application of these advanced techniques in a complex case of a giant Zenker’s diverticulum.
A 59-year-old patient was referred with severe dysphagia due to a giant 9-cm Zenker’s diverticulum. Endoscopy confirmed a large diverticulum associated with a tight upper esophageal stricture. Following multidisciplinary discussion, we proceeded with a modified Z-POEM utilizing the following key techniques:
• Myotomy over the septum for easier access
• Undersaline immersion at the beginning of the procedure to enhance visualization of the submucosal plane
• Tunnel-free approach to allow faster and safer progression
• Extended myotomy across the deepest segment of the cricopharyngeus, both centrally and laterally
• Mucosal flap incision due to the oversized dimensions of the septum
After filling the lumen with normal saline, a mucosal incision was made directly over the septum. Generous submucosal injection was then performed on both sides of the cricopharyngeal muscle, creating submucosal cushions that served as protective barriers during direct myotomy. Because of the limited working space, we continued undersaline immersion and performed dissection in Endocut mode with a needle-type knife.
Once the initial 2 cm of myotomy were completed, the working space widened and we proceeded under CO₂ insufflation. The myotomy was extended to the bottom of the diverticulum and then 2 cm into the esophagus, aiming to reduce recurrence risk. The depth of the myotomy was assessed indirectly by visualizing mucosal discoloration at the diverticulum base.
Given the large septal surface, multiple additional incisions were made along the bottom of the septotomy. The oversized mucosal flap was then incised in Endocut mode using a long L-shaped knife, with efforts to maintain symmetrical trimming on both sides.
Closure was achieved with multiple hemostatic clips. The patient remained NPO and underwent a next-day esophagram showing no leak and no contrast retention.
Recovery was uneventful, and at 6-month follow-up, she is completely asymptomatic, tolerating a full diet.
In conclusion, we demonstrate a modified Z-POEM technique tailored for large Zenker’s diverticula, incorporating:
• undersaline immersion to facilitate early dissection
• a tunnel-free approach for efficient septal division
• deep esophageal extension of the myotomy to prevent recurrence, and
• mucosal flap incision to avoid postoperative food retention