Uploaded August 2026 | Updated September 2026, 3 weeks ago
Sickle Cell Disease and related disorders are caused by mutations genes for the beta subunit of hemoglobin. Adult hemoglobin (HbA) is made up of 2 a-globin & 2 β-globin subunits (whose instructions are in the HBB gene). Fetal hemoglobin (HbF) is made up of 2 a-globin & 2 y-globin subunits (whose instructions are in the HBG genes). β-globin is defective in people with sickle cell disease, ß-thalassemia, & other ß-globinopathies due to one or more of various mutations in the HBB gene.
Structural ß-hemoglobinopathies such as sickle cell anemia (SCA) involve structural changes in ß-globin, whereas β-thalassemias involve reduced ß-globin protein levels. They can both be caused by a variety of mutations in the HBB gene, and some HBB mutations cause both structural β-globin problems and reduced ß-globin levels.
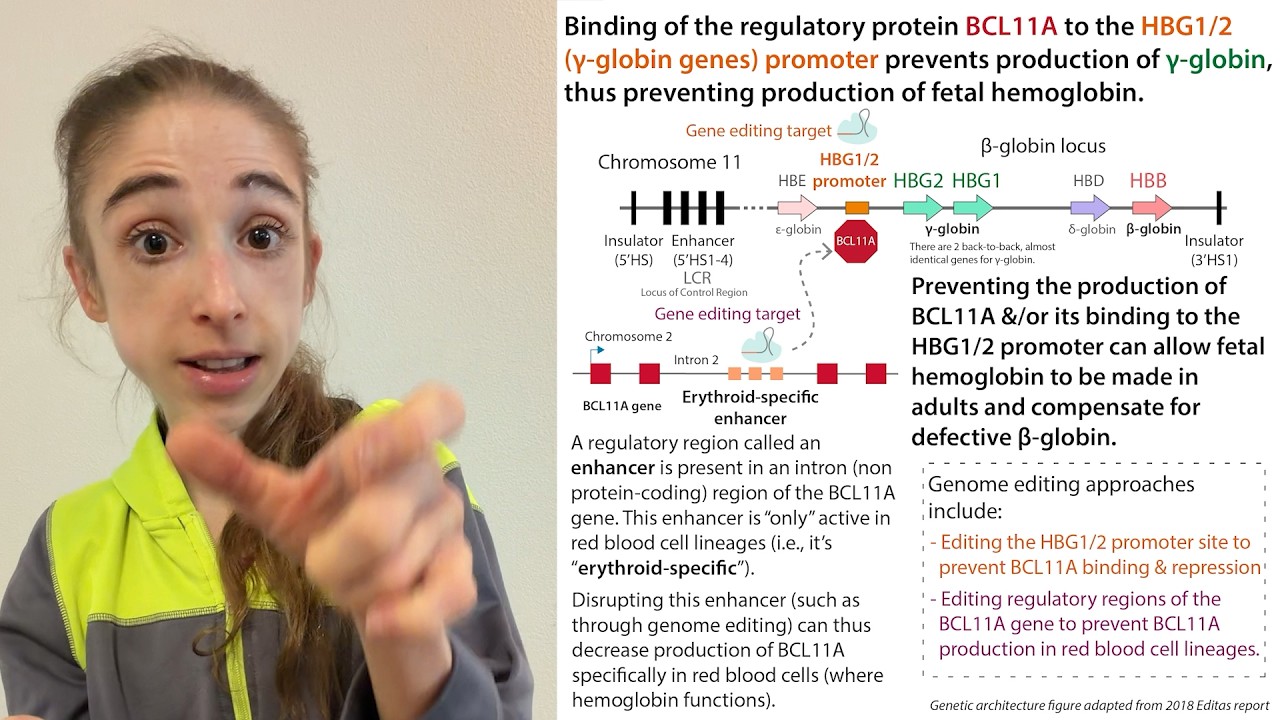
Expression of y-globin is typically switched off after birth through the actions of a regulatory protein called BCL11A. But, if it could be switched back on, it could fill in for any form of faulty and/or missing β-globin.
And this reactivation is what many gene therapies (both approved and in development) seek to achieve! (As well as what the drug hydroxyurea somewhat accomplishes but scientists aren’t quite sure how).
More here: thebumblingbiochemist.com/365-days-of-science/sickle-cell-anemia-beta-thalassemia-other-inherited-hemoglobin-diseases
Fetuses make a “super” version of hemoglobin, HbF, that has a γ subunit instead of a β. Well, it’s super for a fetus dealing with lower “high oxygen” levels but it stops being made after birth because oxygen’s more abundant so it doesn’t need to grab onto it as desperately.
The protein stops being made, but the genetic instructions for making it are still there - written as a gene in chromosome & locked up tight in the nucleus. But it stops being made because another protein, BCL11A, starts being made and it acts as a “brake” to switch off HbF production. (BCL11A is a transcription factor that binds to a regulatory region called a promotor located in front of the γ-globin (HBG) genes (there are 2 back-to-back almost identical HBG genes). By doing so, it 1) recruits repressor proteins including the NuRD (Nucleosome Remodeling and Deacetylase) complex and 2) prevents binding of activator proteins). If doctors could get patients with hemoglobin problems to make this fetal hemoglobin again, by stopping BCL11A from keeping it “off” this might be able to compensate for the faulty adult hemoglobin. It’s the β-globin chain that’s the problem in SCD & β-thalassemias, and it’s the β-globin chain that gets swapped out for a γ-globin chain in fetal hemoglobin (well, I guess it's more the other way around since the fetal hemoglobin is made first . . .).
Something you might be wondering is - don’t babies stop making it for a reason? Will re-expressing it in adults cause problems? Well, it turns out that some people have mutations in BCL11A that cause them to make HbF even as adults, a condition called hereditary persistence of HbF (HPHF) - and they seem perfectly healthy. And people that have SCD or β-thalassemia but also have increased HbF expression have much milder symptoms. By analyzing the genomes of people with HPHF using GWAS (Genome-Wide Association Studies), scientists were able to locate genetic variants in the BCL11A gene as well as in the γ-globin gene (HBG) promoter associated with increased HbF production in adults.
So it seems like disrupting the BCL11A gene to prevent BCL11A from being made and/or keep it from binding the γ-globin (HBG) promoter could offer a viable strategy. Even cooler, γ-globin would be able fill in for any form of faulty and/or missing β-globin. And the editing only needs to be done in the cells that make the blood cells - the hematopoietic stem cells. These stem cells are NOT embryonic stem cells, they’re “adult” stem cells that serve as the source of a continuous supply of mature blood cells. And they are NOT germline cells (those in your eggs or sperm that can get passed down) so any editing done won’t affect any progeny.
So what scientists and doctors have done is remove patients’ hematopoietic stem cells, use CRISPR/Cas to either edit the BCL11A gene or the γ-globin promoter to tamp down BCL11A's tamping down of HbF and sticking the stem cells back in the patient (after chemotherapy has wiped out their remaining hematopoietic stem cells), where they can repopulate the stem cell stock with cells that make the fetal version that can compensate for the faulty versions. This is referred to as "ex vivo" (outside the body) editing, and a form of autologous (auto=self) bone marrow transplant, as opposed to allogeneic (allo=other) transplants which involve transplantation of cells from a healthy donor. More on CRISPR/Cas here: bit.ly/crisprcasscience
Finished in comments