Uploaded August 2026 | Updated September 2026, 2 weeks ago
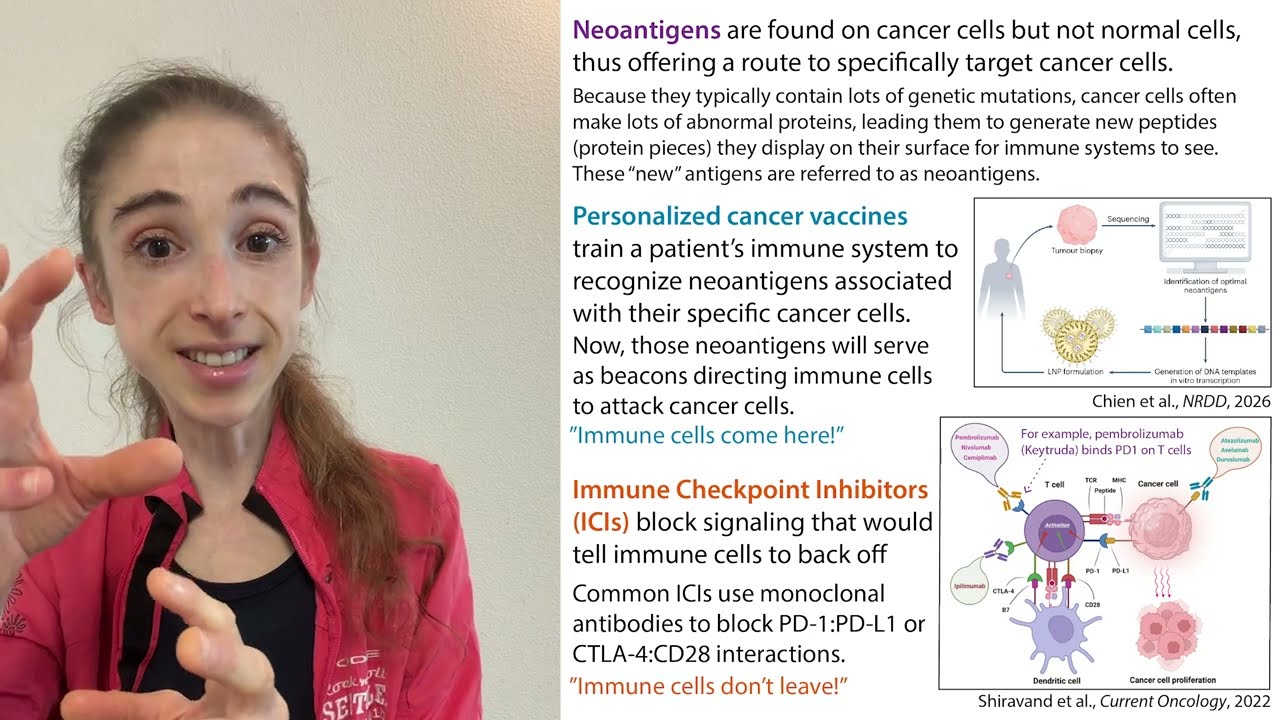
The immune system is really complicated, and I’m way oversimplifying things, but the basic idea of cancer immunotherapy (aka immune-oncology) is to get a person’s immune system to attack their cancer cells. This is challenging because cancer cells are “just” “corrupted” versions of normal self cells. And peoples’ immune systems have multiple safeguards (checkpoints) to prevent their immune systems from attacking normal self cells. That’s super important for preventing autoimmune diseases. But cancer cells can take advantage of these checkpoints to convince the immune system to back off and not attack them. Even if the cancer cells are presenting/displaying signs on their surfaces indicating they’ve gone rogue (such as “neoantigens” – pieces of proteins that healthy cells don’t make but cancer cells make because of the accumulation of lots of mutations).
Cancer immunotherapy often seeks to:
1) Prevent the immune system from getting the “don’t attack” signals from cancer cells (often through the use of checkpoint inhibitors) and/or
2) Get the immune system to receive and/or recognize “attack” signals from cancer cells (such as through the use of personalized tumor vaccines or CAR-T cells)
More here: thebumblingbiochemist.com/biopharmaceutical-sciences
Checkpoint inhibition
Immune checkpoints are safeguards that tell the immune system to back off and not attack a cell. Typically, a type of immune cell receptor sticking off an immune cell surface will bind to a “matching” partner (ligand) displayed on the surface of a normal cell. Kinda like a lock (receptor) and key (ligand) but not quite so simplistic, because the molecules typically change shape a bit when they bind (induced fit).
A couple of the main immune checkpoints are:
• PD-1 (Programmed Cell Death Protein 1) on T cells binding to PD-L1/PD-L2 on other cells
• CTLA-4 (Cytotoxic T-Lymphocyte-Associated Protein 4) on dendritic cells (another type of immune cell) binding to CD80/CD86 on other cells
Immune Checkpoint Inhibitors (ICIs) prevent the above interactions, thereby preventing the immune system from getting the “hey, back off dude!” signal. They’re often in the form of monoclonal antibodies that bind to the receptor or ligand, although alternative blocking molecules and other strategies are being pursued to get around some of the challenges with use of monoclonal antibodies.
A few prominent examples of monoclonal antibody-based ICIs:
• Anti-PD-1 antibodies (antibodies that bind to PD-1 on T cells): pembrolizumab (Keytruda), nivolumab, and cemiplimab
• Anti-CTLA-4 antibodies (antibodies that bind to CTLA-4 on dendritic cells): atezolizumab, avelumab, and durvalumab
Cancer vaccines
Cancer vaccines typically aim to train a person’s immune system to recognize cancer cells as foreign and thus attack it, either as treatment, or to prevent cancer recurrence. Sometimes this is done by taking advantage of the fact that cancer cells often display different molecules on their surfaces than do healthy cells. These “new” molecules are called neoantigens and they can arise due to DNA mutations causing amino acid substitutions, mis-spliced RNA, etc.
The mutations in a cancer cell vary from patient to patient, and thus so do their neoantigens.
Note: There are often early, “driver” mutations that are shared by many cancers, but those mutations often turn off brakes and cell safety nets to allow for the subsequent below-the-radar accumulation of tons of random mutations that can lead to lots of neoantigens being made, but different ones in different people.
Personalized cancer vaccines train a person’s immune system to recognize the neoantigens associated with their tumor. They may be used in conjunction with a checkpoint inhibitor so that the immune cells, once alerted, don’t get the signal to back off.
One example is the mRNA vaccine intismeran autogene, in development by moderna and Merck for use in combination with the checkpoint inhibitor Keytruda (pembrolizumab), a monoclonal antibody that binds to PD-1, thereby blocking PD-1’s binding to PD-L1 and thus preventing T cells from getting the “hey back off dude” message.
In this strategy, a patient’s tumor cells are analyzed to figure out what neoantigens they make. Then, mRNAs with the instructions for (i.e. encoding) multiple of those neoantigens are synthesized (made in the lab), wrapped up (encapsulated) in a nice oily bubble (a lipid nanoparticle, LNP) and delivered to the patient, along with the checkpoint inhibitor.
Finished in comments
The immune system is really complicated, and I’m way oversimplifying things, but the basic idea of cancer immunotherapy (aka immune-oncology) is to get a person’s immune system to attack their cancer cells. This is challenging because cancer cells are “just” “corrupted” versions of normal self cells. And peoples’ immune systems have multiple safeguards (checkpoints) to prevent their immune systems from attacking normal self cells. That’s super important for preventing autoimmune diseases. But cancer cells can take advantage of these checkpoints to convince the immune system to back off and not attack them. Even if the cancer cells are presenting/displaying signs on their surfaces indicating they’ve gone rogue (such as “neoantigens” – pieces of proteins that healthy cells don’t make but cancer cells make because of the accumulation of lots of mutations).
Cancer immunotherapy often seeks to:
1) Prevent the immune system from getting the “don’t attack” signals from cancer cells (often through the use of checkpoint inhibitors) and/or
2) Get the immune system to receive and/or recognize “attack” signals from cancer cells (such as through the use of personalized tumor vaccines or CAR-T cells)
More here: thebumblingbiochemist.com/biopharmaceutical-sciences
Checkpoint inhibition
Immune checkpoints are safeguards that tell the immune system to back off and not attack a cell. Typically, a type of immune cell receptor sticking off an immune cell surface will bind to a “matching” partner (ligand) displayed on the surface of a normal cell. Kinda like a lock (receptor) and key (ligand) but not quite so simplistic, because the molecules typically change shape a bit when they bind (induced fit).
A couple of the main immune checkpoints are:
• PD-1 (Programmed Cell Death Protein 1) on T cells binding to PD-L1/PD-L2 on other cells
• CTLA-4 (Cytotoxic T-Lymphocyte-Associated Protein 4) on dendritic cells (another type of immune cell) binding to CD80/CD86 on other cells
Immune Checkpoint Inhibitors (ICIs) prevent the above interactions, thereby preventing the immune system from getting the “hey, back off dude!” signal. They’re often in the form of monoclonal antibodies that bind to the receptor or ligand, although alternative blocking molecules and other strategies are being pursued to get around some of the challenges with use of monoclonal antibodies.
A few prominent examples of monoclonal antibody-based ICIs:
• Anti-PD-1 antibodies (antibodies that bind to PD-1 on T cells): pembrolizumab (Keytruda), nivolumab, and cemiplimab
• Anti-CTLA-4 antibodies (antibodies that bind to CTLA-4 on dendritic cells): atezolizumab, avelumab, and durvalumab
Cancer vaccines
Cancer vaccines typically aim to train a person’s immune system to recognize cancer cells as foreign and thus attack it, either as treatment, or to prevent cancer recurrence. Sometimes this is done by taking advantage of the fact that cancer cells often display different molecules on their surfaces than do healthy cells. These “new” molecules are called neoantigens and they can arise due to DNA mutations causing amino acid substitutions, mis-spliced RNA, etc.
The mutations in a cancer cell vary from patient to patient, and thus so do their neoantigens.
Note: There are often early, “driver” mutations that are shared by many cancers, but those mutations often turn off brakes and cell safety nets to allow for the subsequent below-the-radar accumulation of tons of random mutations that can lead to lots of neoantigens being made, but different ones in different people.
Personalized cancer vaccines train a person’s immune system to recognize the neoantigens associated with their tumor. They may be used in conjunction with a checkpoint inhibitor so that the immune cells, once alerted, don’t get the signal to back off.
One example is the mRNA vaccine intismeran autogene, in development by moderna and Merck for use in combination with the checkpoint inhibitor Keytruda (pembrolizumab), a monoclonal antibody that binds to PD-1, thereby blocking PD-1’s binding to PD-L1 and thus preventing T cells from getting the “hey back off dude” message.
In this strategy, a patient’s tumor cells are analyzed to figure out what neoantigens they make. Then, mRNAs with the instructions for (i.e. encoding) multiple of those neoantigens are synthesized (made in the lab), wrapped up (encapsulated) in a nice oily bubble (a lipid nanoparticle, LNP) and delivered to the patient, along with the checkpoint inhibitor.
Finished in comments