Uploaded April 2017 | Updated September 2026, 3 hours ago
ASGE Video Forum 2015 from DDW 2015, Washington DC.
Published in Gastrointestinal Endoscopy
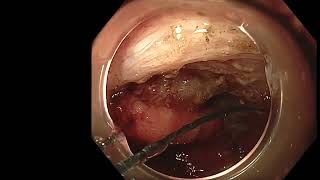
A 63-year-old female patient with a squamous cell carcinoma of the upper esophagus treated with chemo-radiotherapy presented to our department for management of complete dysphagia with inability to swallow saliva. Caloric intake was maintained through a percutaneous gastrostomy. Antegrade endoscopy disclosed complete obliteration of the hypopharynx. Retrograde endoscopy with an ultraslim endoscope through the gastrostomy track showed complete obstruction of the distal esophagus. After multidisciplinary discussion, we decided to attempt an esophageal retrograde recanalization with a dissection knife. Following informed consent, general anesthesia was introduced. The preexisting gastrostomy track was dilated and a 12 mm trocar was placed to allow access to a standard endoscope. Progression of the endoscope towards the distal esophagus showed an obstruction at the level of the Z Line. The submucosal space separating the muscular layers of the esophagus was enlarged by injection of a mixture of a gelatin plasma substitute methylene blue and epinephrine. Progression and recanalization towards the upper esophagus was obtained with an endoscopic submucosal dissection knife using spray coagulation under permanent visual control. CO2 insufflation was used during the whole procedure. Recanalization of the hypopharynx was performed under simultaneous antegrade endoscopic and fluoroscopic guidance with an ultraslim 5.9 mm endoscope loaded with a guidewire. Finally, the rendezvous was achieved and the guidewire was passed into the esophagus and stomach to allow for subsequent 10 mm balloon dilation of the hypopharynx and deployment of a nasogastric tube for maintenance of patency during subsequent endoscopies. A new gastrostomy tube was inserted at the end of the procedure. No major complication was encountered with the exception of slight subcutaneous emphysema without any clinical consequence. During the five months of follow up, serial endoscopies have demonstrated a progressive re-epithelialization of the mid and lower esophagus with persistence of a 6 cm stricture of the upper esophagus and hypopharynx that has been progressively dilated up to 13.5 mm every two weeks. With the assistance of speech physicians the patient now tolerates oral ingestion of liquids. In conclusion, long esophageal strictures secondary to radiation therapy can be treated by means of ESD techniques. While complex, such an approach has the advantage of direct visual control during the whole procedure.
Παρουσίαση του Γαστρεντερολόγου Γιώργου Μαυρογένη στο αμερικανικό συνέδριο γαστρεντερολογίας του 2015.
ASGE Video Forum 2015 from DDW 2015, Washington DC.
Published in Gastrointestinal Endoscopy
A 63-year-old female patient with a squamous cell carcinoma of the upper esophagus treated with chemo-radiotherapy presented to our department for management of complete dysphagia with inability to swallow saliva. Caloric intake was maintained through a percutaneous gastrostomy. Antegrade endoscopy disclosed complete obliteration of the hypopharynx. Retrograde endoscopy with an ultraslim endoscope through the gastrostomy track showed complete obstruction of the distal esophagus. After multidisciplinary discussion, we decided to attempt an esophageal retrograde recanalization with a dissection knife. Following informed consent, general anesthesia was introduced. The preexisting gastrostomy track was dilated and a 12 mm trocar was placed to allow access to a standard endoscope. Progression of the endoscope towards the distal esophagus showed an obstruction at the level of the Z Line. The submucosal space separating the muscular layers of the esophagus was enlarged by injection of a mixture of a gelatin plasma substitute methylene blue and epinephrine. Progression and recanalization towards the upper esophagus was obtained with an endoscopic submucosal dissection knife using spray coagulation under permanent visual control. CO2 insufflation was used during the whole procedure. Recanalization of the hypopharynx was performed under simultaneous antegrade endoscopic and fluoroscopic guidance with an ultraslim 5.9 mm endoscope loaded with a guidewire. Finally, the rendezvous was achieved and the guidewire was passed into the esophagus and stomach to allow for subsequent 10 mm balloon dilation of the hypopharynx and deployment of a nasogastric tube for maintenance of patency during subsequent endoscopies. A new gastrostomy tube was inserted at the end of the procedure. No major complication was encountered with the exception of slight subcutaneous emphysema without any clinical consequence. During the five months of follow up, serial endoscopies have demonstrated a progressive re-epithelialization of the mid and lower esophagus with persistence of a 6 cm stricture of the upper esophagus and hypopharynx that has been progressively dilated up to 13.5 mm every two weeks. With the assistance of speech physicians the patient now tolerates oral ingestion of liquids. In conclusion, long esophageal strictures secondary to radiation therapy can be treated by means of ESD techniques. While complex, such an approach has the advantage of direct visual control during the whole procedure.
Παρουσίαση του Γαστρεντερολόγου Γιώργου Μαυρογένη στο αμερικανικό συνέδριο γαστρεντερολογίας του 2015.