Uploaded April 2017 | Updated September 2026, 23 minutes ago
Percutaneous endoscopic colostomy (PEC) has been established as an alternative method of intestinal decompression and irrigation for functional large bowel obstruction and relapsing sigmoid volvulus. However, postoperative fecal peritonitis secondary to stool leakage, has been reported in 5 to 12% of cases. Prior fixation of the colon to the anterior abdominal wall with the help of a double needle suturing device or T-Fasteners could eventually reduce that risk.
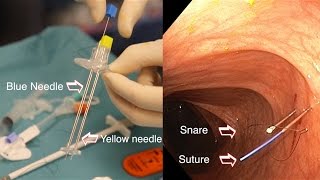
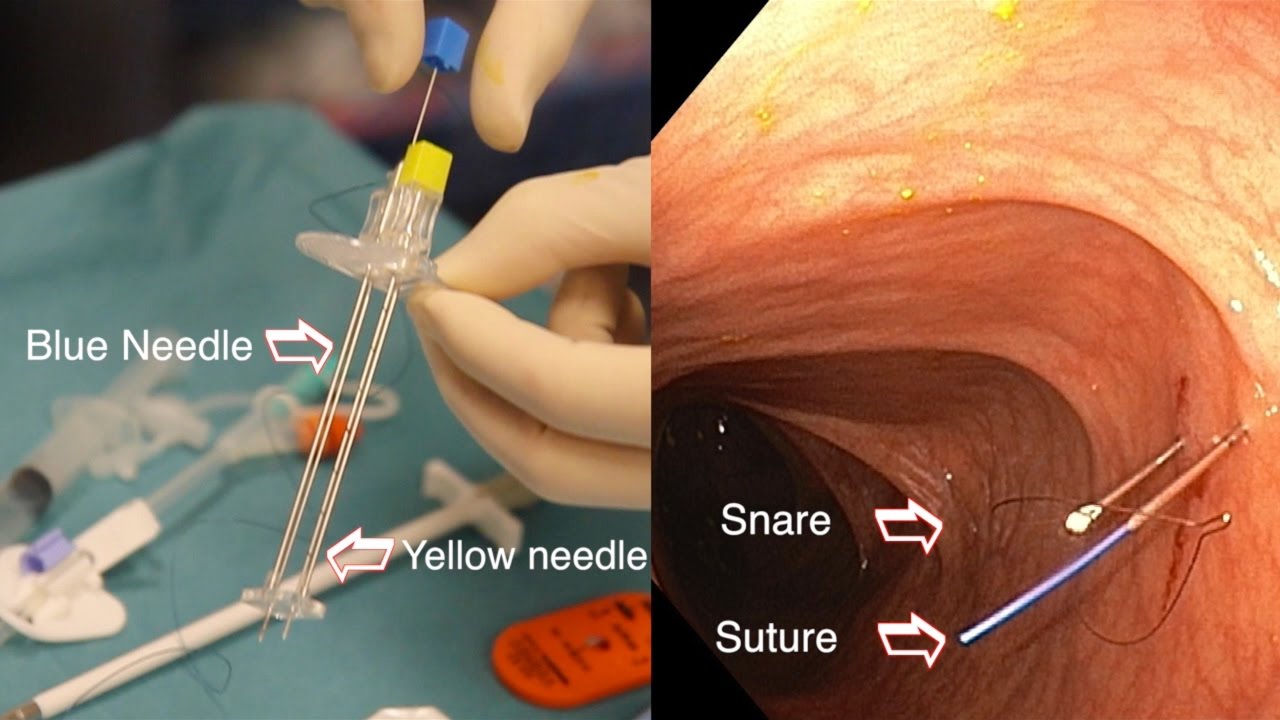
This video presents the case of a 70-year-old patient with a two-month history of diarrhea and painful abdominal distention not responding to medical treatment. He had previously undergone anterior resection for rectal cancer, radiotherapy for bladder cancer and resection of postradiation small intestinal strictures. Clinical examination revealed a cachectic patient with significant distention and high pitched bowel sounds. CT-scan disclosed a 7-cm long stricture of the neo-rectum with upstream dilation of the colon up to 10 cm. Colonoscopy with a slim endoscope revealed a long stricture involving the neo-rectum and sigmoid colon that was not present prior to radiotherapy. Endoscopic treatment with stenting was avoided due to the benign nature of the stricture, its long length, the short distance from the anus and potential side effects such as tenesmus and migration. Furthermore, we estimated that a pneumatic dilation of such a long postradiation stricture carried a significant risk of perforation. The patient was deemed unfit to undergo surgery. Therefore, an introducer type colostomy was suggested, combined with colopexy, using a dedicated suturing device which has been designed for percutaneous endoscopic gastropexy (Freka Pexact Gastrostomy system, Fresenius Kabi, UK).
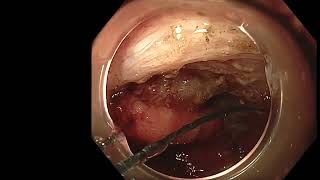
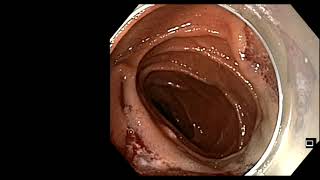
Prophylactic antibiotics were administrated prior to the procedure. The left colon was distended with CO2, and the site of puncture was located by means of light transillumination and finger indentation, proximally to the stenotic segment. Local anesthesia was administrated and the colon was punctured with the injection needle in order to confirm good positioning. Then, we performed colopexy with the help of the introducer needle which was inserted in the lumen of the colon. A small incision was made between sutures, and a trocar with a peel-away sheath was introduced through the abdominal wall into the colon. The trocar was removed, a 15 French PEG tube was progressed through the sheath, and the balloon was inflated with 5 ml of sterile water. The peel away sheath was removed, and the retaining plate was placed.
The patient recovered uneventfully and was discharged after 24 hours. Antibiotics were prolonged for 5 more days and the sutures were removed after 10 days. We advised the patient to administer at least 50 ml of water 3 times per day in order to avoid obstruction of the tube by stools, and to exsufflate the distended abdomen by opening the valve of the tube as needed. When necessary, larger quantities of water were administrated in order to facilitate defecation.
After two months of regular use of the tube for both decompression and irrigation, the symptoms progressively improved. The patient was readmitted for replacement of the balloon catheter with a standard pull through gastrostomy tube. However, the patient denied further endoscopic treatment, despite the risk of recurrence. The colostomy tube was removed and the fistulous tract closed two days later. At 6 months of follow up the patient presents mild abdominal distention and subsequent episodes of obstruction have been managed successfully with the combination of pancreatic enzyme supplements and osmotic laxatives.
In conclusion, PEC with the introducer method combined with colopexy, may be used as salvage therapy for colonic decompression and irrigation of selected cases of mechanical obstruction. Fixation of the colon to the abdominal wall may decrease the risk of postoperative peritonitis, secondary to stool leakage or to tube dislocation.
Percutaneous endoscopic colostomy (PEC) has been established as an alternative method of intestinal decompression and irrigation for functional large bowel obstruction and relapsing sigmoid volvulus. However, postoperative fecal peritonitis secondary to stool leakage, has been reported in 5 to 12% of cases. Prior fixation of the colon to the anterior abdominal wall with the help of a double needle suturing device or T-Fasteners could eventually reduce that risk.
This video presents the case of a 70-year-old patient with a two-month history of diarrhea and painful abdominal distention not responding to medical treatment. He had previously undergone anterior resection for rectal cancer, radiotherapy for bladder cancer and resection of postradiation small intestinal strictures. Clinical examination revealed a cachectic patient with significant distention and high pitched bowel sounds. CT-scan disclosed a 7-cm long stricture of the neo-rectum with upstream dilation of the colon up to 10 cm. Colonoscopy with a slim endoscope revealed a long stricture involving the neo-rectum and sigmoid colon that was not present prior to radiotherapy. Endoscopic treatment with stenting was avoided due to the benign nature of the stricture, its long length, the short distance from the anus and potential side effects such as tenesmus and migration. Furthermore, we estimated that a pneumatic dilation of such a long postradiation stricture carried a significant risk of perforation. The patient was deemed unfit to undergo surgery. Therefore, an introducer type colostomy was suggested, combined with colopexy, using a dedicated suturing device which has been designed for percutaneous endoscopic gastropexy (Freka Pexact Gastrostomy system, Fresenius Kabi, UK).
Prophylactic antibiotics were administrated prior to the procedure. The left colon was distended with CO2, and the site of puncture was located by means of light transillumination and finger indentation, proximally to the stenotic segment. Local anesthesia was administrated and the colon was punctured with the injection needle in order to confirm good positioning. Then, we performed colopexy with the help of the introducer needle which was inserted in the lumen of the colon. A small incision was made between sutures, and a trocar with a peel-away sheath was introduced through the abdominal wall into the colon. The trocar was removed, a 15 French PEG tube was progressed through the sheath, and the balloon was inflated with 5 ml of sterile water. The peel away sheath was removed, and the retaining plate was placed.
The patient recovered uneventfully and was discharged after 24 hours. Antibiotics were prolonged for 5 more days and the sutures were removed after 10 days. We advised the patient to administer at least 50 ml of water 3 times per day in order to avoid obstruction of the tube by stools, and to exsufflate the distended abdomen by opening the valve of the tube as needed. When necessary, larger quantities of water were administrated in order to facilitate defecation.
After two months of regular use of the tube for both decompression and irrigation, the symptoms progressively improved. The patient was readmitted for replacement of the balloon catheter with a standard pull through gastrostomy tube. However, the patient denied further endoscopic treatment, despite the risk of recurrence. The colostomy tube was removed and the fistulous tract closed two days later. At 6 months of follow up the patient presents mild abdominal distention and subsequent episodes of obstruction have been managed successfully with the combination of pancreatic enzyme supplements and osmotic laxatives.
In conclusion, PEC with the introducer method combined with colopexy, may be used as salvage therapy for colonic decompression and irrigation of selected cases of mechanical obstruction. Fixation of the colon to the abdominal wall may decrease the risk of postoperative peritonitis, secondary to stool leakage or to tube dislocation.