Uploaded March 2020 | Updated September 2026, 43 minutes ago
Use of dual clip and band countertraction for wide field ESD of the gastric angulus for multifocal low grade dysplasia.

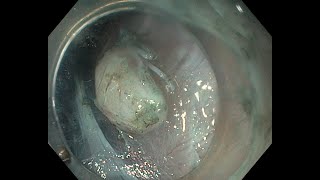



![Intramuscular tunneling as a rescue strategy during POEM for short-segment submucosal fibrosis.
Intramuscular tunneling as a rescue strategy during POEM for short-segment submucosal fibrosis. Mavrogenis et al. Clinical Endoscopy 2026.
Severe submucosal fibrosis during peroral endoscopic myotomy (POEM) may increase the risk of complications. Conventional strategies to overcome fibrosis include the use of slim endoscopes, tapered-tip caps, and water-jet knives, as well as the creation of a second tunnel [1]. Notably, intramuscular tunneling has emerged as a valuable rescue technique [2].
In this video, we demonstrate the use of intramuscular tunneling in a patient with extreme fibrosis at the tunnel entry site. Following mucosal incision, the muscular layer was immediately encountered because of the absence of a discernible submucosal plane (Fig. 1). Next, the dissection plane was directed between the thick fibers of the circular muscle layer (Fig. 2). Repeated saline injections and gentle pressure with a tapered-tip cap were used to maintain the intramuscular plane, and spray coagulation facilitated separation of the circular muscle fibers. Proper orientation was preserved by maintaining an intact layer of circular muscle fibers around the tunnel and avoiding extension toward the longitudinal muscle layer. The intramuscular tunnel was extended for approximately 4 cm, enabling bypassing of the fibrotic segment. Re-entry into the conventional submucosal plane between the mucosa and muscularis propria was achieved, enabling progression to the cardia. Partial and subsequent full-thickness myotomy was completed uneventfully. Post-procedural computed tomography (CT) esophagography confirmed intact closure without leakage. During the 9 months of follow-up, the patient experienced a 10-kg weight gain and an improvement in the Eckardt score from 9 to 1. In conclusion, experienced endoscopists may consider intramuscular tunneling in cases of short-segment fibrosis when the circular muscle layer is sufficiently thick to permit intramuscular dissection. Attention should be given to thorough esophageal cleaning before tunneling, avoiding mediastinal entry, and minimizing excessive insufflation or injections outside the intramuscular plane. Overall, in cases of long-segment fibrosis, creation of a second tunnel may represent a more appropriate strategy.
References
1. Nabi Z, Ramchandani M, Chavan R, Basha J, Reddy M, Darisetty S, Reddy ND. Double tunnel technique reduces technical failure during POEM in cases with severe submucosal fibrosis. Endosc Int Open 2021;9:E1335-E1341.
2. Mavrogenis G, Song LMWK, Bazerbachi F. In the thick of it: peroral endoscopic myotomy with intramuscular tunneling in end-stage achalasia. Ann Gastroenterol 2021;34:756. Intramuscular tunneling as a rescue strategy during POEM for short-segment submucosal fibrosis.](https://i.ytimg.com/vi/A6sbTn19RpY/mqdefault.jpg)


