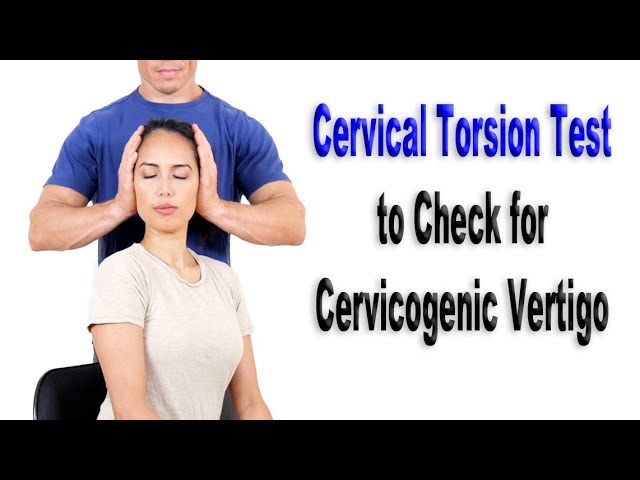
Cervical Torsion Test to Evaluate for Cervicogenic Vertigo or Dizziness Fauquier ENT 2024-10-08 | Transient dizziness or vertigo that occurs with head movements is often attributed to a vestibular problem like BPPV (youtu.be/G3xPpkGPEvE). However, cervical spine problems that have nothing to do with the inner ear can also elicit vertigo attacks with head movements. Additional symptoms that suggest a cervicogenic source of dizziness instead of the inner ear include history of headache, neck pain, and limited cervical range of motion. There are bedside tests which can further suggest the diagnosis of cervicogenic vertigo, especially if the Dix-Hallpike test (youtu.be/G3xPpkGPEvE) for BPPV comes back normal. These tests require the head to be kept still to prevent any activation of the inner ear balance system. As such, any test movements that trigger dizziness is thus isolated to the cervical spine as the source of the vertigo. The cervical torsion test is performed with the patient seated on a swivel chair with the hip and knees flexed to 90 degrees. The patient closes both eyes and the examiner fixates the patient's head in neutral position. The patient is then asked to actively rotate the body 45 to 90 degrees to one side and hold for 30 seconds. When returned to neutral position, the patient may open the eyes. The test is then repeated in the opposite direction, again with the eyes first closed.The test is positive if the patient reports any dizziness and/or any other symptoms other than normal. Other symptoms include visual disturbances, speech disturbances, motion sickness, nausea, trouble swallowing, lightheadedness, tinnitus, headache and/or paresthesias during or immediately after the test.The cervical torsion test can also be performed laying down with the head on a pillow. The patient closes both eyes and the examiner fixates the patient's head in neutral position. The patient is then asked to actively rotate the body 45 to 90 degrees to one side and hold for 30 seconds. When returned to neutral position, the patient may open the eyes. The test is then repeated in the opposite direction, again with the eyes first closed.If cervicogenic vertigo is suspected, please see your healthcare professional for further treatment guidance. A neurologist or a spine specialist are the doctors who specialize in treating this condition. There are also home exercises that can be performed to treat cervicogenic vertigo, but should only be performed if there is no pain and no numbness present.Please be aware that this test has a specificity of 98.5%. Sensitivity has not been determined yet which makes the clinical use of this test unknown at this time.Other tests for cervicogenic vertigo:• Head Neck Differentiation Test: youtu.be/zOPMJhYYCbQ• Smooth Pursuit Neck Torsion Test: youtu.be/RAyRDYGEpLsHome exercises for cervcigeic vertigo: youtu.be/29rXWlO-evM• Intro (0:00)• Sitting Cervical Torsion Test (0:50)• Supine Cervical Torsion Test (1:42)• Conclusion (2:11)References:Evaluation of paraclinical tests in the diagnosis of cervicogenic dizziness. Otology & neurotology, 35(10), 1858-1865. 2014. pubmed.ncbi.nlm.nih.gov/25058834Normative responses to clinical tests for cervicogenic dizziness: Clinical cervical torsion test and head-neck differentiation test. Physical Therapy, 100(1), 192-200. 2020. pubmed.ncbi.nlm.nih.gov/31584656Video created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
3 Tests for Cervicogenic Vertigo or Dizziness Fauquier ENT 2024-10-21 | Transient dizziness or vertigo that occurs with head movements is often attributed to a vestibular problem like BPPV (youtu.be/G3xPpkGPEvE). However, cervical spine problems that have nothing to do with the inner ear can also elicit vertigo attacks with head movements. Additional symptoms that suggest a cervicogenic source of dizziness instead of the inner ear include history of headache, neck pain, and limited cervical range of motion. There are three bedside tests which can further suggest the diagnosis of cervicogenic vertigo, especially if the Dix-Hallpike test (youtu.be/G3xPpkGPEvE) for BPPV comes back normal. These tests require the head to be kept still to prevent any activation of the inner ear balance system. As such, any test movements that trigger dizziness is thus isolated to the cervical spine as the source of the vertigo. For all three tests, the head is kept still to prevent any activation of the inner ear balance system. As such, any test movements that trigger dizziness is thus isolated to the cervical spine as the source of the vertigo.The first test is called the cervical torsion test. The cervical torsion test is performed with the patient seated on a swivel chair with the hip and knees flexed to 90 degrees. The patient closes both eyes and the examiner fixates the patient's head in neutral position as shown. The patient is then asked to actively rotate the body 45 to 90 degrees to one side and hold for 30 seconds. When returned to neutral position, the patient may open the eyes. The test is then repeated in the opposite direction, again with the eyes first closed. The test is positive if the patient reports any dizziness and/or any other symptoms other than normal. Other symptoms include visual disturbances, speech disturbances, motion sickness, nausea, trouble swallowing, lightheadedness, tinnitus, headache and/or paresthesias during or immediately after the test.The head neck differentiation test is similar to the cervical torsion test. The head neck differentiation test is performed with the patient seated on a swivel chair with the hip and knees flexed to 90 degrees. The patient closes both eyes and the examiner fixates the patient's head in neutral position as shown. The patient is then asked to actively rotate the body 45 degrees with the help of the legs to the left and then right side in an alternating fashion at a metronome pace of 60 beats per minute for at least 30 seconds. The test is positive if the patient reports any dizziness and/or any other symptoms other than normal. Other symptoms include visual disturbances, speech disturbances, motion sickness, nausea, trouble swallowing, lightheadedness, tinnitus, headache and/or paresthesias during or immediately after the test.The final test for cervicogenic vertigo is smooth pursuit neck torsion test. The smooth pursuit neck torsion test is performed by first having the patient sitting on a swivel chair. While the patient’s head is kept still in a neutral position, the patient is to track the examiner’s finger which is moved slowly side to side in a horizontal direction. While keeping the head still, the test is then repeated with the body rotated 45 degrees to one side. And then repeated again with the body rotated 45 degrees to the opposite side. The test is positive if dizziness is triggered in the rotated position compared to neutral. If cervicogenic vertigo is suspected, please see your healthcare professional for further treatment guidance. A neurologist or a spine specialist are the doctors who specialize in treating this condition. There are also home exercises that can be performed to treat cervicogenic vertigo, but should only be performed if there is no pain and no numbness present.Home exercises for cervcogeic vertigo: youtu.be/29rXWlO-evMDix Hallpike Maneuver to Diagnose BPPV: youtu.be/G3xPpkGPEvEMeniere's Disease: youtu.be/qrk7OyAB_ssVisual Vertigo: youtu.be/IhJ_SlCnWb4• Intro (0:00)• Smooth Pursuit Neck Torsion Test (0:50)• Head Neck Differentiation Test (1:45)• Smooth Pursuit Neck Torsion Test (2:39)References:Smooth pursuit neck torsion test: a specific test for cervical dizziness. Am J Otol. 1998 Jan;19(1):76-81. pubmed.ncbi.nlm.nih.gov/9455954Normative responses to clinical tests for cervicogenic dizziness: Clinical cervical torsion test and head-neck differentiation test. Physical Therapy, 100(1), 192-200. 2020. pubmed.ncbi.nlm.nih.gov/31584656Evaluation of paraclinical tests in the diagnosis of cervicogenic dizziness. Otology & neurotology, 35(10), 1858-1865. 2014. pubmed.ncbi.nlm.nih.gov/25058834Video created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Smooth Pursuit Neck Torsion Test to Check for Cervicogenic Vertigo or Dizziness Fauquier ENT 2024-10-20 | Transient dizziness or vertigo that occurs with head movements is often attributed to a vestibular problem like BPPV (youtu.be/G3xPpkGPEvE). However, cervical spine problems that have nothing to do with the inner ear can also elicit vertigo attacks with head movements. Additional symptoms that suggest a cervicogenic source of dizziness instead of the inner ear include history of headache, neck pain, and limited cervical range of motion. There are bedside tests which can further suggest the diagnosis of cervicogenic vertigo, especially if the Dix-Hallpike test (youtu.be/G3xPpkGPEvE) for BPPV comes back normal. These tests require the head to be kept still to prevent any activation of the inner ear balance system. As such, any test movements that trigger dizziness is thus isolated to the cervical spine as the source of the vertigo. The smooth pursuit neck torsion test is performed by first having the patient sitting on a swivel chair. While the patient’s head is kept still in a neutral position, the patient is to track the examiner’s finger which is moved slowly side to side in a horizontal direction. While keeping the head still, the test is then repeated with the body rotated 45 degrees to one side. And then repeated again with the body rotated 45 degrees to the opposite side. The test is positive if dizziness is triggered in the rotated position compared to neutral.If cervicogenic vertigo is suspected, please see your healthcare professional for further treatment guidance. A neurologist or a spine specialist are the doctors who specialize in treating this condition. There are also home exercises that can be performed to treat cervicogenic vertigo, but should only be performed if there is no pain and no numbness present.Please be aware that this test has a sensitivity of 90% and specificity of 91%.Other tests for cervicogenic vertigo:• Cervical Torsion Test: youtu.be/o1c7SlFe3Js• Head Neck Differentiation Test: youtu.be/zOPMJhYYCbQHome exercises for cervcogeic vertigo: youtu.be/29rXWlO-evM• Intro (0:00)• Smooth Pursuit Neck Torsion Test (0:50)• Conclusion (1:38)References:Smooth pursuit neck torsion test: a specific test for cervical dizziness. Am J Otol. 1998 Jan;19(1):76-81. pubmed.ncbi.nlm.nih.gov/9455954Video created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Head Neck Differentiation to Check for Cervicogenic Vertigo or Dizziness Fauquier ENT 2024-10-09 | Transient dizziness or vertigo that occurs with head movements is often attributed to a vestibular problem like BPPV (youtu.be/G3xPpkGPEvE). However, cervical spine problems that have nothing to do with the inner ear can also elicit vertigo attacks with head movements. Additional symptoms that suggest a cervicogenic source of dizziness instead of the inner ear include history of headache, neck pain, and limited cervical range of motion. There are bedside tests which can further suggest the diagnosis of cervicogenic vertigo, especially if the Dix-Hallpike test (youtu.be/G3xPpkGPEvE) for BPPV comes back normal. These tests require the head to be kept still to prevent any activation of the inner ear balance system. As such, any test movements that trigger dizziness is thus isolated to the cervical spine as the source of the vertigo. The head neck differentiation test is performed with the patient seated on a swivel chair with the hip and knees flexed to 90 degrees. The patient closes both eyes and the examiner fixates the patient's head in neutral position as shown. The patient is then asked to actively rotate the body 45 degrees with the help of the legs to the left and then right side in an alternating fashion at a metronome pace of 60 beats per minute for at least 30 seconds. The test is positive if the patient reports any dizziness and/or any other symptoms other than normal. Other symptoms include visual disturbances, speech disturbances, motion sickness, nausea, trouble swallowing, lightheadedness, tinnitus, headache and/or paresthesias during or immediately after the test.If cervicogenic vertigo is suspected, please see your healthcare professional for further treatment guidance. A neurologist or a spine specialist are the doctors who specialize in treating this condition. There are also home exercises that can be performed to treat cervicogenic vertigo, but should only be performed if there is no pain and no numbness present.Please be aware that this test has a specificity of 90%. Sensitivity has not been determined yet which makes the clinical use of this test unknown at this time.Other tests for cervicogenic vertigo:• Cervical Torsion Test: youtu.be/o1c7SlFe3Js• Smooth Pursuit Neck Torsion Test: youtu.be/RAyRDYGEpLsHome exercises for cervcigeic vertigo: youtu.be/29rXWlO-evM• Intro (0:00)• Head Neck Differentiation Test (0:50)• Conclusion (1:44)References:Normative responses to clinical tests for cervicogenic dizziness: Clinical cervical torsion test and head-neck differentiation test. Physical Therapy, 100(1), 192-200. 2020. pubmed.ncbi.nlm.nih.gov/31584656Video created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Optokinetic Training: Cruise Ship Corridor #2 Fauquier ENT 2024-09-17 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQWalking down the hallway of a cruise ship.Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Notched Audio White Noise Sampler of Different Notch Widths in the Treatment for Tinnitus Fauquier ENT 2024-09-10 | There are many possible ways to treat tinnitus. Effective sound therapy like pink noise or white noise can significantly reduce the perceived loudness of tinnitus. Notched audio, however, is the next step beyond generic sound therapy and is tailored precisely to an individual's specific tinnitus frequency. Simply put, notched sound or audio therapy is one type of tinnitus treatment that can reduce the intensity or loudness of tinnitus by listening to special audio tracks on any device whether phone, car stereo, music player, etc. The key change that must be made to the audio track, however, is that the specific tinnitus frequency that is experienced by a given individual must be completely removed from the audio track. By removing this specific sound frequency or "notching" the audio, the tinnitus itself then supplies the missing frequency sound in the audio track.The second variable that needs to be addressed is how "wide" the frequency notching should be. Standard width is one octave, but can be as small as 0.25 or as wide as 4 octaves. The video demonstrates different sized widths when notched at 7000 Hz and how it affects the sound of a standard white noise.The theory goes that when an individual turns off the notched audio sound, the brain will hear an absence of sound (obviously)... but more importantly may ALSO turn off the tinnitus sound. In practice, the tinnitus sound does not turn off for most, but does reduce in many tinnitus sufferers.For more information on notched audio and how it works: youtu.be/nz8Dn5t5LdgSample notched audio of white noise at different frequencies:youtu.be/EJ-SVaU5ScoFor more info and free notched audio files you can download:https://www.CheckHearing.org/notchedsound.phpTinnitus matching here:checkhearing.org/tinnitusmatching.phpDifferent types of white noise:youtu.be/aiyh2j-BfkQAcoustic CR Neuromodulation to Treat Tinnitus:youtu.be/vxp8Q0rs7hMIntro (0:00)0.25 Width (0:22)0.5 Width (0:27)1.0 Width (0:32)1.25 Width (0:37)1.5 Width (0:42)2.0 Width (0:47)3.0 Width (0:53)Still haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwAReferences:The Windowed Sound Therapy: A New Empirical Approach for an Effective Personalized Treatment of Tinnitus. Int Tinnitus J. 2009;15(1):51-61. pubmed.ncbi.nlm.nih.gov/19842347Customized notched music training reduces tinnitus loudness. Communicative & Integrative Biology 3:3, 274-277; May/June 2010 pubmed.ncbi.nlm.nih.gov/20714412Short and Intense Tailor-Made Notched Music Training against Tinnitus: The Tinnitus Frequency Matters. PLoS ONE 6(9): e24685. journals.plos.org/plosone/article?id=10.1371/journal.pone.0024685#s2Clinical trial on tonal tinnitus with tailor-made notched music training. BMC Neurol. 2016; 16: 38. ncbi.nlm.nih.gov/pmc/articles/PMC4797223Counteracting tinnitus by acoustic coordinated reset neuromodulation. Restorative Neurology and Neuroscience 30 (2012) 137–159. pubmed.ncbi.nlm.nih.gov/22414611#tinnitus #notchedaudio #audionotching #audionotch #tinnitustreatment
Dix Hallpike Maneuver to Diagnose BPPV - What Side and What Type for Proper Treatment Fauquier ENT 2024-09-09 | Video shows how vertigo due to BPPV is diagnosed using the Dix-Hallpike maneuver. Furthermore the different types of BPPV causing different eye twitches (nystagmus) also shown (0:56) as well as what maneuver will work best to treat.Keep in mind that one additional step to fully diagnose BPPV is not shown in the video. Called fatiguability, the maneuver should be performed 2 or 3 times on the side that is positive to see if the vertigo attack severity diminishes when repeated more than once. If the vertigo does NOT fatigue with repetition, the dizziness is due to something else... usually brain/spine problem and not BPPV!!!For more info: https://www.FauquierENT.net/BPPV.htmWatch how the inner ear balance system works here:youtube.com/watch?v=YMIMvBa8XGsFlowchart to help diagnose dizziness in general: fauquierent.net/dizziness/dizzy1.htm4 Different Types of BPPV (0:25)POSTERIOR canal BPPV treated by Epley maneuver here:youtu.be/VmCItD9nDfYPOSTERIOR canal BPPV treated by Foster Half-Somersault here:youtube.com/watch?v=Wez9SZJ7ABsLATERAL canal BPPV treated by Lempert maneuver here:youtu.be/HCXU4IcTpr4SUPERIOR canal BPPV treated by Deep Head-Hanging here:youtu.be/ijyx5tVeaVoVideo on Meniere's Disease:youtube.com/watch?v=qrk7OyAB_ssVideo produced by Dr. Chris Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#bppv #vertigo #dizziness #homeremedy #epley #medicalanimation
A Day in the Life of an ENT Surgeon. CPK Shawn - Pop Like This Fauquier ENT 2024-09-01 | Just for fun!Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Optokinetic Training: Cruise Ship Corridor Fauquier ENT 2024-08-22 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQWalking down the hallway of a cruise ship.Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Example HINTs Findings with Stroke and Vestibular Neuritis Causing Persistent Dizziness Fauquier ENT 2024-07-27 | In order to understand this video, you must understand how HINTs is performed and utilized. Watch this intro video on HINTs: youtu.be/iIgezzbbFgg• Normal (0:07 )• Vestibular Neuritis (0:47)• Stroke (1:26)Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
HINTs Exam for Acute Vestibular Syndrome (Continuous Dizziness): Stroke or Vestibular Neuritis? Fauquier ENT 2024-07-26 | The HINTs examination, an acronym for Head Impulse, Nystagmus, and Test of Skew, is a cluster of 3 bedside tests used to evaluate a patient with acute onset dizziness that is continuously present, even when still. These tests can quickly differentiate between an inner ear vestibular problem versus central vertigo, which may be due to a stroke.The head impulse test starts by flexing the patient’s head down slightly and moving their head slowly back and forth while having their eyes maintain fixed focus straight ahead. The head is then moved quickly and unexpectedly to one side while the patient tries to maintain straight target focus. The test is considered normal if the eyes stay focused on target without slippage.However, if the eyes are dragged off the straight ahead target, even briefly, the test would be considered abnormal suggesting an inner ear vestibular problem. Please note that there needs to be a minimum 50% weakness of the inner ear vestibular system in order for this test to be positive.Next, check the patient’s eyes for any nystagmus which are involuntary repetitive eye twitching. To evaluate for nystagmus, have the patient move the eyes in all the cardinal directions: left, right, up, and down.Normally, nystagmus should be absent. However, if nystagmus is present, note which direction the eye is beating towards. The direction of nystagmus is defined by the direction of the quick phase.An inner ear or vestibular cause for dizziness is suggested if the nystagmus is horizontal and the direction remains the same regardless of which direction the eye is looking. A neurologic cause for dizziness is suggested if the nystagmus changes direction with eye movement. Neurologic cause for dizziness is also suggested if vertical or torsional nystagmus is present in any eye position.The skew test, also known as the cover test, involves the patient focusing straight on a target while the clinician covers and uncovers each eye, observing for any vertical movement of the uncovered eye. Normally, the uncovered eye remains steady. However, if it moves up or down, this indicates a vertical skew deviation, which can suggest a serious brain disorder involving the brainstem or cerebellum instead of a more benign cause due to an inner ear vestibular problem.Collectively, when all 3 HINTs exams are performed in a dizzy patient, it is 95% accurate in identifying a central cause like stroke or peripheral origin like vestibular neuritis.Accuracy is further increased when performing a HINTs-plus test when adding a fourth sign which is the presence of a one-sided, new-onset hearing loss which would suggest labyrinthitis.• Intro (0:00)• Head Impulse (0:29)• Nystagmus (1:40)• Test of Skew (3:10)• HINTs Interpretation (3:46)Video created by Dr. Christopher Chang:https://www.FauquierENT.netReferencesUsage of the HINTS exam and neuroimaging in the assessment of peripheral vertigo in the emergency department. J Otolaryngol Head Neck Surg. 2018;47:54. ncbi.nlm.nih.gov/pmc/articles/PMC6131950HINTS to diagnose stroke in the acute vestibular syndrome: three-step bedside oculomotor examination more sensitive than early MRI diffusion-weighted imaging. Stroke. 2009 Nov;40(11):3504-10. ncbi.nlm.nih.gov/pmc/articles/PMC4593511H.I.N.T.S. to Diagnose Stroke in the Acute Vestibular Syndrome—Three-Step Bedside Oculomotor Exam More Sensitive than Early MRI DWI. Stroke. 2009 Nov; 40(11): 3504–3510. ncbi.nlm.nih.gov/pmc/articles/PMC4593511Actor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Types of Nystagmus Due to Stroke vs Vestibular Neuritis Causing Persistent Dizziness or Vertigo Fauquier ENT 2024-07-25 | When a patient experiences sudden dizziness that lasts continuously for several hours if not longer, the primary concern is whether the dizziness is due to an inner ear problem or a neurologic issue.One of the first things to quickly and easily check for is something called nystagmus, or involuntary repetitive eye twitching. To evaluate for nystagmus, have the patient move the eyes in all the cardinal directions: left, right, up, and down.Normally, nystagmus should be absent. However, if nystagmus is present, note which direction the eye is beating towards. The direction of nystagmus is defined by the direction of the quick phase.An inner ear or vestibular cause for dizziness is suggested if the nystagmus is horizontal and the direction remains the same regardless of which direction the eye is looking. A neurologic cause for dizziness is suggested if the nystagmus changes direction with eye movement. Neurologic cause for dizziness is also suggested if vertical or torsional nystagmus is present in any eye position.Of course, if nystagmus is absent in a dizzy patient, it does not eliminate either a neurologic or vestibular cause for dizziness. But, when this test is combined with a head impulse and skew test, diagnosing a stroke can be as accurate as an MRI scan! Of note, the type of stroke this test identifies is a cerebellar stroke which accounts for only 2% of all strokes.Head Impulse Test: youtu.be/B09sz3prKBISkew Test: youtu.be/CdnQNUarZr8HINTs Test: youtu.be/iIgezzbbFggVideo created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Skew Test to Evaluate Dizziness Due to Possible Stroke Fauquier ENT 2024-07-25 | The skew test, also known as the cover test, is a simple test used to determine whether a patient’s acute onset and continuous dizziness is due to a neurological disorder such as a stroke. The test involves a dizzy patient focusing straight ahead on a fixed target while the clinician covers and uncovers each eye, observing for any vertical movement of the uncovered eye. Normally, the uncovered eye remains steady. However, if the eye moves up or down, this indicates a vertical skew deviation, which can suggest a serious brain disorder involving the brainstem or cerebellum instead of a more benign cause due to an inner ear vestibular problem.Keep in mind that the skew test has a very low sensitivity of around 15%, but high specificity of about 98%… which basically means that this test is more reliable at correctly identifying those dizzy patients without a neurological condition than those with one.But, when this test is combined with a head impulse and nystagmus test (HINTs), diagnosing a stroke can be as accurate as an MRI scan!Head Impulse Test: youtu.be/B09sz3prKBINystagmus Test: youtu.be/k9M9Th3mXe4HINTs Test: youtu.be/iIgezzbbFggReferenceAcute vestibular syndrome: is skew deviation a central sign? J Neurol. 2022; 269(3): 1396–1403.Video created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
40Hz Light and Sound (Peak 10kHz) Gamma Brainwave Used in MIT Research to Prevent Dementia Fauquier ENT 2024-07-23 | *Make sure the video settings are set to 2160p60!!! Or you will not see the 40Hz light flickering.*Studies at MIT and elsewhere are producing mounting evidence that light flickering and sound clicking at the gamma brain rhythm frequency of 40 hertz can reduce Alzheimer’s disease (AD) progression and treat symptoms in human volunteers as well as lab mice.Why 40 Hz? Light and sound sensory gamma stimulation increases 40Hz power and synchrony in the brains of mice, that prompts a particular type of neuron to release peptides. These short peptide protein signals drive specific neuronal processes that promote increased amyloid and tau clearance via the glymphatic system. Because amyloid and tau protein buildup in the brain is one of the main findings in Alzheimer's dementia, reducing such "toxic" protein buildup is thought to possibly decrease risk for dementia development and potentially even treat it.TED talk on this topic here: youtube.com/watch?v=AS0K0XOMNwAIn 2016, MIT researchers discovered that brain wave gamma frequency (40Hz) power and synchrony are substantially weaker in Alzheimer’s model mice and may also be in patients. They experimented in mice by stimulating gamma rhythms with completely non-invasive 40Hz flashes of visible light. In 2019, they showed that the flashes dubbed GENUS for Gamma ENtrainment Using Sensory, stimuli protected against neurodegeneration. In 2019, the researchers showed that 40Hz sound stimulation works in mice too. They found that GENUS preserved both memory and cognitive performance..In 2022, they published results of pilot Phase 1 and Phase 2A human clinical studies showing that audio and visual GENUS was safe, well tolerated and successful in increasing 40Hz power and coherence around the brain. Moreover, treated participants showed reduced brain atrophy, improved sleep patterns and improvement on face-name association memory after three months compared to untreated controls. The results have been so promising, a new startup company, Cognito Therapeutics, has been created by the MIT researchers.This video is for educational purposes only. Please consult your doctor before engaging in brain wave technology! Preliminary results suggest watching and listening for 1 hour every day.ResearchMultisensory gamma stimulation promotes glymphatic clearance of amyloid. Nature 627, 149–156 (2024). doi.org/10.1038/s41586-024-07132-6Gamma frequency sensory stimulation in mild probable Alzheimer’s dementia patients: Results of feasibility and pilot studies. PLOS ONE. Dec 2022. doi.org/10.1371/journal.pone.0278412Gamma Entrainment Binds Higher-Order Brain Regions and Offers Neuroprotection. Neuron. Volume 102, Issue 5, 5 June 2019, Pages 929-943.e8. sciencedirect.com/science/article/pii/S0896627319303460?via%3DihubMulti-sensory Gamma Stimulation Ameliorates Alzheimer’s-Associated Pathology and Improves Cognition. Cell. Volume 177, Issue 2, 4 April 2019, Pages 256-271.e22sciencedirect.com/science/article/pii/S0092867419301631?via%3DihubVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
40Hz Light and Sound (Flat 10kHz) Gamma Brainwave Used in MIT Research to Prevent Dementia Fauquier ENT 2024-07-23 | *Make sure the video settings are set to 2160p60!!! Or you will not see the 40Hz light flickering.*Studies at MIT and elsewhere are producing mounting evidence that light flickering and sound clicking at the gamma brain rhythm frequency of 40 hertz can reduce Alzheimer’s disease (AD) progression and treat symptoms in human volunteers as well as lab mice.Why 40 Hz? Light and sound sensory gamma stimulation increases 40Hz power and synchrony in the brains of mice, that prompts a particular type of neuron to release peptides. These short peptide protein signals drive specific neuronal processes that promote increased amyloid and tau clearance via the glymphatic system. Because amyloid and tau protein buildup in the brain is one of the main findings in Alzheimer's dementia, reducing such "toxic" protein buildup is thought to possibly decrease risk for dementia development and potentially even treat it.TED talk on this topic here: youtube.com/watch?v=AS0K0XOMNwAIn 2016, MIT researchers discovered that brain wave gamma frequency (40Hz) power and synchrony are substantially weaker in Alzheimer’s model mice and may also be in patients. They experimented in mice by stimulating gamma rhythms with completely non-invasive 40Hz flashes of visible light. In 2019, they showed that the flashes dubbed GENUS for Gamma ENtrainment Using Sensory, stimuli protected against neurodegeneration. In 2019, the researchers showed that 40Hz sound stimulation works in mice too. They found that GENUS preserved both memory and cognitive performance..In 2022, they published results of pilot Phase 1 and Phase 2A human clinical studies showing that audio and visual GENUS was safe, well tolerated and successful in increasing 40Hz power and coherence around the brain. Moreover, treated participants showed reduced brain atrophy, improved sleep patterns and improvement on face-name association memory after three months compared to untreated controls. The results have been so promising, a new startup company, Cognito Therapeutics, has been created by the MIT researchers.This video is for educational purposes only. Please consult your doctor before engaging in brain wave technology! Preliminary results suggest watching and listening for 1 hour every day.ResearchMultisensory gamma stimulation promotes glymphatic clearance of amyloid. Nature 627, 149–156 (2024). doi.org/10.1038/s41586-024-07132-6Gamma frequency sensory stimulation in mild probable Alzheimer’s dementia patients: Results of feasibility and pilot studies. PLOS ONE. Dec 2022. doi.org/10.1371/journal.pone.0278412Gamma Entrainment Binds Higher-Order Brain Regions and Offers Neuroprotection. Neuron. Volume 102, Issue 5, 5 June 2019, Pages 929-943.e8. sciencedirect.com/science/article/pii/S0896627319303460?via%3DihubMulti-sensory Gamma Stimulation Ameliorates Alzheimer’s-Associated Pathology and Improves Cognition. Cell. Volume 177, Issue 2, 4 April 2019, Pages 256-271.e22sciencedirect.com/science/article/pii/S0092867419301631?via%3DihubVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Waiting... and Waiting... and Waiting for Anesthesia... Come on Eileen Fauquier ENT 2024-07-23 | Just for fun!Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
ENT Doctor Transformation from Clinic to OR. 911 Emergency Song, Budots Dance Fauquier ENT 2024-07-20 | Just for fun! Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#budotsdance #emergencydance
Lymphatic Massage for Head & Neck to Reduce Swelling or Lymphedema Fauquier ENT 2024-07-05 | Lymphedema or soft tissue swelling of the head and neck is common after an illness or after treatment for throat cancer whether surgery and/or radiation therapy. Although compression is commonly used for arm or leg lymphedema, compression is not possible for the head and neck region. Rather lymphatic massage is utilized instead. Beyond massage, exercise is important as muscles act as a pump to stimulate and squeeze the lymphatic vessels to get fluid moving out. In this video, we will focus on lymphatic massage. Performing the massage first thing in the morning is best for head and neck lymphedema because laying flat all night negates gravity’s influence in helping to keep this region drained when upright during the day.The overall goal of manual lymph drainage for head and neck lymphedema is to get the fluid moving out of the head and neck area and down towards another region like the chest and armpit areas. Make sure to use as much of a flat hand and your whole palm or your all your fingers and not just a couple fingers or your fingertips. You want to try to use as much surface area as possible against your skin to get the most benefit. Using lotion or some type massage oil is helpful as well to minimize skin friction.It's best to perform lymphatic massage sitting upright instead of laying down in order to take advantage of gravity to move the fluid down and out of the head and neck area. Do not perform lymphatic massage in any area that is painful or if you have any new surgical incisions or scars that are not fully healed, otherwise you risk opening up the wound. Before we begin, make sure to take deep breaths in and out using your diaphragm. Also known as belly breaths, make sure you continue these deep breaths in and out throughout the entire lymphatic massage sequence.Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#lymphaticmassage #lymphedema
Head Impulse Test to Check for Vestibular Hypofunction Causing Dizziness Fauquier ENT 2024-07-03 | Normally with head movement, the eyes and the inner ear balance system work together to ensure that the eyes can maintain a fixed position gaze regardless of head position. Known as the vestibulo-ocular reflex, we know that the right inner ear balance system pushes the eyes to the left when we move our heads to the right… and the left inner ear balance system pushes the eyes to the right when we move our heads to the left.For patients suffering from dizziness, an examination called the head impulse test takes advantage of this information to help determine if there is a weakness in the connection between the inner ear balance system and the eyes.The head impulse test (aka head thrust test) first described in 1988 starts by flexing the patient’s head down slightly and moving their head slowly back and forth while having their eyes maintain fixed focus straight ahead. The head is then moved quickly and unexpectedly to one side while the patient tries to maintain straight target focus. The test is considered normal if the eyes stay focused on target without slippage.However, if the eyes are dragged off the straight ahead target, even briefly, the test would be considered abnormal. Video demonstrates normal and abnormal head impulse test.Nystagmus Test: youtu.be/k9M9Th3mXe4Skew Test: youtu.be/CdnQNUarZr8HINTs Test: youtu.be/iIgezzbbFggVideo created by Dr. Christopher Chang:https://www.FauquierENT.netActor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwAReferences:A clinical sign of canal paresis. Arch Neurol (1988) 45:737–9. pubmed.ncbi.nlm.nih.gov/3390028A clinical evaluation of head impulse testing. Clin Otolaryngol Allied Sci 1998; 23:117. pubmed.ncbi.nlm.nih.gov/9597280Optimizing the sensitivity of the head thrust test for identifying vestibular hypofunction. Phys Ther 2004; 84:151. pubmed.ncbi.nlm.nih.gov/14744205A clinical evaluation of head impulse testing. Clin Otolaryngol Allied Sci 1998; 23(2): 117-22. pubmed.ncbi.nlm.nih.gov/9597280More than a 50% canal paresis is needed for the head impulse test to be positive. Otol Neurotol 2005; 26(2): 318-9. pubmed.ncbi.nlm.nih.gov/15793428#dizziness #vertigotreatment #vertigo
Optokinetic Training: Library Walk (Complex) Fauquier ENT 2024-07-03 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQWalking around inside a university library with stacks completely filled with books.Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Escalator Fauquier ENT 2024-07-03 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Subway Fauquier ENT 2024-07-03 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Library Walk (Simple) Fauquier ENT 2024-06-30 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQWalking around inside a local library with stacks not completely filled with books.Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Free Online Eye Tracking Program (Saccade Eye or Visual Tracking Testing or Exercise): 3 Methods! Fauquier ENT 2024-06-28 | There is a free online visual or eye tracking program that displays a target circle in random locations which can also be used for visual tracking exercises: https://www.CheckHearing.org/saccadesTest.phpVisual or eye tracking, is the ability to move the eyes quickly and smoothly in any direction, whether reading or following a moving object. It's a fine motor skill that's important for many daily activities, including reading, writing, drawing, playing, and sports. When visual tracking is abnormal, it can lead to difficulties with normal activities and even dizziness, a type of visual vertigo. In these cases, visual tracking exercises can help restore normal eye tracking and resolve symptoms.There are 3 ways to perform eye tracking exercises.Method #1 (0:54) is to keep the head still with the nose pointing straight at the middle of the screen. While keeping the head still, follow the targets with the eyes only.Method #2 (1:12) is to start by looking at the center. When the target appears, look at the target with the eyes first, then turn the head such that you are both looking at the target and the head is also pointed at the target. When the target disappears, return to the center.Method #3 (1:39) is to start by looking at the center. When the target appears, look at the target with the eyes first, then turn your head such that you are both looking at the target and the head is also pointed at the target. When the target disappears, you remain in this position until the next target appears. You do NOT return to the center when the target disappears.Methods #2 and #3 can be considered types of optokinetic exercises as there is both head and eye movements, whereas method #1 is mainly a visual exercise given the lack of head movement.There is also a custom setting (2:07) in order to change the speed/duration of the test as well as vary the size and color of the target circle.Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Optokinetic Stripes Red & Black Right to Left Moving at Different Speeds Fauquier ENT 2024-06-28 | Video showing red and black stripes moving right to left at different speeds used in the treatment of Mal de Debarquement Syndrome (MdDS) or Visual Vertigo with metronome at 10 bpm. This video is meant for those whom single color optokinetic stripes do help, but this may provide additional visual stimuli for a more intense training.Optokinetic Training for Visual Vertigo:youtu.be/rZok6mZnhwQMdDs Treatment:Known as optokinetic head roll exercises, the moving stripes are utilized to help resolve symptoms in up to 70% of patients who suffer from this condition within 5 days.Video on How to Perform Head Roll Exercise: youtu.be/a4402WcaQA4The video is exactly 5 minutes long which is the recommended duration to perform these exercises up to 8 times a day. Also played is a metronome at 10 bpm which is the recommended duration of one head roll cycle. Finally, do play this on as large a screen as possible and make sure the optokinetic stripes fill at least 80% of your vision!To optimize clarity, the video was made at 4K resolution at 60fps.Full playlist of red/black thin/thick stripes moving either right/left:youtube.com/playlist?list=PLblLJazSSA3R1UjH-rLu6kYTPGh5Vfb-rHead Roll ExerciseFirst, figure out the dominant direction of your rocking or swaying. Now this can be a little tricky because the rocking or swaying is moving back and forth… But, most people can identify a dominant side to their swaying or rocking. So even though you're going back and forth a lot of times, you'll feel more of a pull in one direction versus the other. See if you can identify what that direction is. If you can’t, you're going to just pick one side and go with that one. If after a few days, there is no improvement, then you can switch sides. Once you have picked a side, you will set the optokinetic stimulation stripes to go in the opposite direction. SO for example, if your sway is right side dominant, you will set the optokinetic stripes to move in the left direction. Once you have picked a direction, hold the screen in front of the eyes such that it fills at least 80% of your visual field.You do not want it too far from your eyes, but close enough that it really fills up most your vision.There is a metronome audio in this video set to 10 beats per minute. Each beat is going to represent one full cycle of head movement.Without turning the head, you will first bring one ear down towards the same side shoulder. Then move the head back to neutral position. Then move the opposite ear towards the opposite shoulder, then back to neutral position. This completes one cycle.Try to make the head movement as one continuous smooth motion without stopping at any point.Each session should be performed for 3-5 minutes. Make sure to observe your physical reactions to the exercise and if you start to feel really ill, then stop and take some grounding breaths and try again later.In order to be truly helpful, this exercise needs to be performed up to 8 times a day.If this exercise helps, you should start to feel improvement within 5 days. If you don't have an improvement in the first five days, then either this exercise will not work for you OR you picked the wrong side to begin with in which case, you would repeat this entire exercise again, but in the opposite direction.Reference:Readaptation of the vestibulo-ocular reflex relieves the mal de debarquement syndrome. Neurol. 2014 Jul 15:5:124. pubmed.ncbi.nlm.nih.gov/25076935Sham-Controlled Study of Optokinetic Stimuli as Treatment for Mal de Debarquement Syndrome. Front Neurol. 2018 Oct 25:9:887. pubmed.ncbi.nlm.nih.gov/30410464Optokinetic motion sickness and pseudo-Coriolis effects induced by moving visual stimuli. Acta Otolaryngol 76(5): 339-348. 1973. pubmed.ncbi.nlm.nih.gov/4543918Prevention of overt motion sickness by incremental exposure to otherwise highly stressful coriolis accelerations. Aerospace Medicine 40(2): 142-148. 1969. pubmed.ncbi.nlm.nih.gov/5304382Mal de debarquement. Arch Otolaryngol Head Neck Surg 125(6): 615-620. 1999. pubmed.ncbi.nlm.nih.gov/10367916Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#mdds #maldedebarquement #chronicdizziness #dizziness
Optokinetic Stripes Red & Black Moving in Opposite Directions Fauquier ENT 2024-06-28 | Video showing red and black stripes moving in opposite directions and different speeds used in the treatment of Mal de Debarquement Syndrome (MdDS) or Visual Vertigo with metronome at 10 bpm. This video is meant for those whom single color optokinetic stripes do help, but this may provide additional visual stimuli for a more intense training.Optokinetic Training for Visual Vertigo:youtu.be/rZok6mZnhwQMdDs Treatment:Known as optokinetic head roll exercises, the moving stripes are utilized to help resolve symptoms in up to 70% of patients who suffer from this condition within 5 days.Video on How to Perform Head Roll Exercise: youtu.be/a4402WcaQA4The video is exactly 5 minutes long which is the recommended duration to perform these exercises up to 8 times a day. Also played is a metronome at 10 bpm which is the recommended duration of one head roll cycle. Finally, do play this on as large a screen as possible and make sure the optokinetic stripes fill at least 80% of your vision!To optimize clarity, the video was made at 4K resolution at 60fps.Full playlist of red/black thin/thick stripes moving either right/left:youtube.com/playlist?list=PLblLJazSSA3R1UjH-rLu6kYTPGh5Vfb-rHead Roll ExerciseFirst, figure out the dominant direction of your rocking or swaying. Now this can be a little tricky because the rocking or swaying is moving back and forth… But, most people can identify a dominant side to their swaying or rocking. So even though you're going back and forth a lot of times, you'll feel more of a pull in one direction versus the other. See if you can identify what that direction is. If you can’t, you're going to just pick one side and go with that one. If after a few days, there is no improvement, then you can switch sides. Once you have picked a side, you will set the optokinetic stimulation stripes to go in the opposite direction. SO for example, if your sway is right side dominant, you will set the optokinetic stripes to move in the left direction. Once you have picked a direction, hold the screen in front of the eyes such that it fills at least 80% of your visual field.You do not want it too far from your eyes, but close enough that it really fills up most your vision.There is a metronome audio in this video set to 10 beats per minute. Each beat is going to represent one full cycle of head movement.Without turning the head, you will first bring one ear down towards the same side shoulder. Then move the head back to neutral position. Then move the opposite ear towards the opposite shoulder, then back to neutral position. This completes one cycle.Try to make the head movement as one continuous smooth motion without stopping at any point.Each session should be performed for 3-5 minutes. Make sure to observe your physical reactions to the exercise and if you start to feel really ill, then stop and take some grounding breaths and try again later.In order to be truly helpful, this exercise needs to be performed up to 8 times a day.If this exercise helps, you should start to feel improvement within 5 days. If you don't have an improvement in the first five days, then either this exercise will not work for you OR you picked the wrong side to begin with in which case, you would repeat this entire exercise again, but in the opposite direction.Reference:Readaptation of the vestibulo-ocular reflex relieves the mal de debarquement syndrome. Neurol. 2014 Jul 15:5:124. pubmed.ncbi.nlm.nih.gov/25076935Sham-Controlled Study of Optokinetic Stimuli as Treatment for Mal de Debarquement Syndrome. Front Neurol. 2018 Oct 25:9:887. pubmed.ncbi.nlm.nih.gov/30410464Optokinetic motion sickness and pseudo-Coriolis effects induced by moving visual stimuli. Acta Otolaryngol 76(5): 339-348. 1973. pubmed.ncbi.nlm.nih.gov/4543918Prevention of overt motion sickness by incremental exposure to otherwise highly stressful coriolis accelerations. Aerospace Medicine 40(2): 142-148. 1969. pubmed.ncbi.nlm.nih.gov/5304382Mal de debarquement. Arch Otolaryngol Head Neck Surg 125(6): 615-620. 1999. pubmed.ncbi.nlm.nih.gov/10367916Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#mdds #maldedebarquement #chronicdizziness #dizziness
Optokinetic Stripes Red & Black Left to Right Moving at Different Speeds Fauquier ENT 2024-06-28 | Video showing red and black stripes moving left to right at different speeds used in the treatment of Mal de Debarquement Syndrome (MdDS) or Visual Vertigo with metronome at 10 bpm. This video is meant for those whom single color optokinetic stripes do help, but this may provide additional visual stimuli for a more intense training.Optokinetic Training for Visual Vertigo:youtu.be/rZok6mZnhwQMdDs Treatment:Known as optokinetic head roll exercises, the moving stripes are utilized to help resolve symptoms in up to 70% of patients who suffer from this condition within 5 days.Video on How to Perform Head Roll Exercise: youtu.be/a4402WcaQA4The video is exactly 5 minutes long which is the recommended duration to perform these exercises up to 8 times a day. Also played is a metronome at 10 bpm which is the recommended duration of one head roll cycle. Finally, do play this on as large a screen as possible and make sure the optokinetic stripes fill at least 80% of your vision!To optimize clarity, the video was made at 4K resolution at 60fps.Full playlist of red/black thin/thick stripes moving either right/left:youtube.com/playlist?list=PLblLJazSSA3R1UjH-rLu6kYTPGh5Vfb-rHead Roll ExerciseFirst, figure out the dominant direction of your rocking or swaying. Now this can be a little tricky because the rocking or swaying is moving back and forth… But, most people can identify a dominant side to their swaying or rocking. So even though you're going back and forth a lot of times, you'll feel more of a pull in one direction versus the other. See if you can identify what that direction is. If you can’t, you're going to just pick one side and go with that one. If after a few days, there is no improvement, then you can switch sides. Once you have picked a side, you will set the optokinetic stimulation stripes to go in the opposite direction. SO for example, if your sway is right side dominant, you will set the optokinetic stripes to move in the left direction. Once you have picked a direction, hold the screen in front of the eyes such that it fills at least 80% of your visual field.You do not want it too far from your eyes, but close enough that it really fills up most your vision.There is a metronome audio in this video set to 10 beats per minute. Each beat is going to represent one full cycle of head movement.Without turning the head, you will first bring one ear down towards the same side shoulder. Then move the head back to neutral position. Then move the opposite ear towards the opposite shoulder, then back to neutral position. This completes one cycle.Try to make the head movement as one continuous smooth motion without stopping at any point.Each session should be performed for 3-5 minutes. Make sure to observe your physical reactions to the exercise and if you start to feel really ill, then stop and take some grounding breaths and try again later.In order to be truly helpful, this exercise needs to be performed up to 8 times a day.If this exercise helps, you should start to feel improvement within 5 days. If you don't have an improvement in the first five days, then either this exercise will not work for you OR you picked the wrong side to begin with in which case, you would repeat this entire exercise again, but in the opposite direction.Reference:Readaptation of the vestibulo-ocular reflex relieves the mal de debarquement syndrome. Neurol. 2014 Jul 15:5:124. pubmed.ncbi.nlm.nih.gov/25076935Sham-Controlled Study of Optokinetic Stimuli as Treatment for Mal de Debarquement Syndrome. Front Neurol. 2018 Oct 25:9:887. pubmed.ncbi.nlm.nih.gov/30410464Optokinetic motion sickness and pseudo-Coriolis effects induced by moving visual stimuli. Acta Otolaryngol 76(5): 339-348. 1973. pubmed.ncbi.nlm.nih.gov/4543918Prevention of overt motion sickness by incremental exposure to otherwise highly stressful coriolis accelerations. Aerospace Medicine 40(2): 142-148. 1969. pubmed.ncbi.nlm.nih.gov/5304382Mal de debarquement. Arch Otolaryngol Head Neck Surg 125(6): 615-620. 1999. pubmed.ncbi.nlm.nih.gov/10367916Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#mdds #maldedebarquement #chronicdizziness #dizziness
Optokinetic Training: Farmers Market Walk Fauquier ENT 2024-06-25 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQThis farmer's market was recorded in France.Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Costco Walk Fauquier ENT 2024-06-24 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Supermarket Walk Fauquier ENT 2024-06-24 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Target Store Walk (Department Store) Fauquier ENT 2024-06-23 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Bridge Drive (Advanced Pattern Complexity) Fauquier ENT 2024-06-23 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Bridge Drive (Intermediate Pattern Complexity) Fauquier ENT 2024-06-23 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Highway Drive (4 Lane to 2 Lane) Fauquier ENT 2024-06-22 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Highway Drive with Dividers Fauquier ENT 2024-06-22 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Bridge Drive (Simple Suspension) Fauquier ENT 2024-06-22 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Tunnel Drive (4 short and 1 long) Fauquier ENT 2024-06-22 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQThese tunnel shots were all obtained in Colorado. The long tunnel starts at (1:10).Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training: Daytime City Walk Fauquier ENT 2024-06-22 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQThis city walk was performed in downtown Denver, CO.Looking up skyscraper #1 (18:56), skyscraper #2 (19:56), and skyscraper #3 (20:25).Playlist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Visual Tracking Exercises - 7 Different Patterns, 3 Different Speeds Fauquier ENT 2024-06-19 | Slow speed starts at (0:05). Medium speed starts at (10:12). Fast speed starts at (15:25). Exercises should be performed 15 minutes per day, 5 times per week. Best done on a full size screen... the bigger, the better (not a mobile device).Visual tracking, also known as eye tracking, is the ability to move your eyes quickly and smoothly in any direction, whether reading or following a moving object. It's a fine motor skill that's important for many daily activities, including reading, writing, drawing, playing, and sports. When visual tracking is abnormal, it can lead to difficulties with normal activities and even dizziness, a type of visual vertigo.For example, an ice hockey player may have trouble tracking where the puck is. A student may constantly lose his place while reading a book.Visual tracking exercises can help restore normal eye tracking.These exercises should first be performed at slow speech (0:05) with nose pointed straight at the center of the screen. The eyes should try to smoothly follow the moving circle. Once the circle is able to be easily tracked smoothly (no blurring, dizziness, losing track of the circle), the speed can be increased to medium (10:12), and then fast (15:25).A variety of patterns are shown including zig-zag vertical, star, figure 8, circle, zig-zag horizontal, horizontal bouncing, and vertical bouncing.To further increase the difficulty of these exercises, try placing the head in different positions (other than straight ahead):• Nose pointed at right edge of screen• Nose pointed at left edge of screen• Nose pointed at top edge of screen• Nose pointed at bottom edge of screen• Moving head up and down while doing the exercises• Moving head side to side while doing the exercisesYou can increase the difficulty with saccade eye exercises which utilizes a circle that briefly appears on the screen in random locations: checkhearing.org/saccadesTest.phpVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA
Optokinetic Training: Highway Drive (2 Lanes) Fauquier ENT 2024-06-17 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training - Forest Drive (Including Switchbacks) Fauquier ENT 2024-06-17 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Gaze Stability Exercises to Treat Dizziness/Vertigo Due to Vestibular Hypofunction Fauquier ENT 2024-06-14 | Dizziness or vertigo due to vestibular hypofunction secondary to labryrinthitis, vestibular neuritis, Meniere’s disease, concussion, or some other condition can often lead to chronic dizziness. Such dizziness may persist even if the underlying disease state has resolved leading to a baseline sense of imbalance. For such patients, the goal is to help the brain recalibrate taking into account the vestibular hypofunction and reset the overall balance system to the new “settings” so to speak.The main way to accomplish this are gaze stability exercises. Initially, these exercises should all be performed while sitting still. Incidentally, these exercises can also be performed to help recover from a concussion injury.Keep in mind when performing these exercises, that the goal is to try and move your head as fast as possible without your vision blurring. The goal is 120-240 head shakes per minute. If you start to get visual blurring, slow the head movements down. But the goal is to always go as fast as possible, right up to the limit when visual blurring occurs.1) VOR x 1 (0:58)2) VOR Far (1:55)3) VOR x 2 (2:34)4) Gaze Stability Reading (3:12)5) Imaginary VOR (3:46)6) Two Target Head Turns (4:32)7) Difficulty Progression (5:25)You can download a sheet of random letters for the gaze stability reading here:payhip.com/b/eq5lFOnline visual gaze exercises can be performed here: https://www.CheckHearing.org/saccadesTest.phpVestibular Therapist:Amy McMillin, PT yout.com/@treatdizzinessathome2023https://www.CustomCareRehab.comReferences:Vestibular Rehabilitation for Peripheral Vestibular Hypofunction: An Updated Clinical Practice Guideline From the Academy of Neurologic Physical Therapy of the American Physical Therapy Association. pubmed.ncbi.nlm.nih.gov/34864777Actor Credit:MJ Gordon @marinjayden Certified Yoga Alliance Instructor (RYP500, RPYT, Yin) Certified Fitness Instructor NCEPhttps://www.MJ-Gordon.comVideo created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#vertigotreatment #dizzinessrelief #vestibulartherapy #concussion
Optokinetic Training - Casino Environment Fauquier ENT 2024-06-12 | For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfSpecial thanks to @WalkingAmbience for use of this excerpted video. Check out the full length video here: youtube.com/watch?v=AAeK-7AWqFAAlso take a look at other casino videos @WalkingAmbience Edited by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training - City Nighttime Walking Fauquier ENT 2024-06-12 | This video taken in LasVegas. For more information on how to use youtube videos to perform optokinetic training, please watch this video: youtu.be/rZok6mZnhwQPlaylist of other optokinetic training videos: youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfSpecial thanks to @WalkingAmbience for use of this excerpted video. Check out the full length video here: youtube.com/watch?v=_edGkcnHlRMAlso take a look at other casino videos @WalkingAmbience Edited by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#optokinetictraining
Optokinetic Training to Treat Visually Induced Dizziness or Vertigo (Vestibular Rehabilitation) Fauquier ENT 2024-06-09 | Optokinetic training is a method to treat people who have dizziness in visually stimulating places like busy city street, casinos, grocery stores, or airports. In such spatial visually busy environments, symptoms include nausea, dizziness, or just feeling off. Some triggers for people who suffer from visual vertigo include nausea and dizziness when going to Costco, pulling into a parking lot, trying to walk across the parking lot, and feeling dizzy or uncomfortable when seeing traffic moving past while setting still at a red light. So with optokinetic training, there are two goals... Desensitize to a visually busy environment before even going into it and use of the somatasensory or touch system by paying attention to our bodies to help with grounding. Watch the video to see how all this works!• Intro (0:00)• What is Optokinetic Training (0:56)• What are symptoms of visual vertigo (1:19)• Why does visual vertigo happen? (2:13)• What does optokinetic training do (4:22)• Example (4:34)• Who benefits from optokinetic training? (5:39)• How to do optokinetic training (6:03)• Conclusion (11:32)Online visual gaze exercises can be performed here: https://www.CheckHearing.org/saccadesTest.phpVestibular Physical Therapist:Amy Mcmillin, PT @treatdizzinessathome2023 Owner of Custom Care Rehab in OhioWebsite: customcarerehab.comEmail: treatdizzinessathome@gmail.com Purchasable download of OptoKinetic Training with Full instructions: payhip.com/b/OAQhSPlaylist of OptoKinetic videos : youtube.com/playlist?list=PLblLJazSSA3T4L5LWXuaS3OYWEETr5ARfEdited by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#vertigo #visualvertigo #motionsensitive #vertigotreatment #dizziness #vestibulartherapy #optokinetictraining
Exercises and Postures to Help with Swallowing Problems: Basic Swallow Therapy for Dysphagia Fauquier ENT 2024-06-06 | There are three fundamental exercises and two basic postures that swallow therapists use to help a patient overcome swallowing difficulties as part of a comprehensive treatment plan.The swallowing exercises are performed in order to strengthen the swallowing muscles to more effectively swallow without problems. Just like any other muscle in the body, targeted exercise will make a muscle stronger and more efficient.Positioning maneuvers are to help with swallow, but is more geared towards helping to close off the airway thereby minimizing risk of aspiration.The first technique is the Masako maneuver, which improves the function of the back of the throat during swallowing. For this exercise, the tongue is stuck out and placed between the teeth. Then you swallow while keeping your tongue held between the teeth the entire time. Perform 10 times, three times a day.The second exercise is the Mendelsohn Maneuver which is a bit more difficult. When you swallow normally, the Adam's apple or your larynx moves upward. You can feel this movement by feeling for the notch on the top part of your voicebox and then swallowing. So when food or liquids go down with a swallow, the voicebox moves upward, and then back down as the swallow is completed.With the Mendelsohn maneuver, you squeeze the throat muscles as tightly together as possible the moment the voicebox raises to its highest level during a swallow. The tongue is pressed tightly against the roof of the mouth. Hold this position for 3-5 seconds before relaxing. When holding the throat in this tightly squeezed position, you are holding your breath which is what naturally occurs during a swallow. This exercise just accentuates and strengthens that natural breath holding during swallow. Perform 5-10 Mendelsohn maneuvers three times a day.The third strengthening exercise is to help with the swallow timing. Called a supraglottic swallow, there are 3 steps. First hold your breath. Step 2, swallow. Finally step 3, cough after the swallow is completed.Now let’s talk about the 2 positioning maneuvers to help with swallow. Remember, these maneuvers help to close the airway to prevent aspiration of food or liquids. With both positions, remember to ALWAYS sit upright when you eat. It's very important to make sure that the person with the swallowing disorder is sitting up at 90 degrees every single time they swallow anything. It’s easier to do this in a chair, but if they happen to be in a bed, make sure to still sit up in the bed at 90 degrees or as far as they can go.The first and most common position technique is called a chin tuck. Right before initiating a swallow, tuck the chin down to the chest. Once the head is down, swallow hard and fast, keeping the head all the way down the entire time. Once the swallow has been completed, then bring the head back up. By bringing the chin down to the chest, it helps to protect the airway as it opens the throat up in a way that makes it easier to swallow without aspiration. For some patients, this is the only they are able to swallow safely. The second positioning maneuver helps mostly with people who have had a stroke that affects one side of their throat and vocal cords. For example, if someone had a stroke on the left side of the body, it is common to also have issues with the left side of the throat and voicebox. In this situation, swallowing should occur with the head turned towards the affected side…. the side that is not working. When swallowing in this position, food and liquids preferentially goes down the opposite good side as the head turn essentially narrows closed the bad side of the throat. Beyond, these basic swallowing strategies to help improve swallow, be sure to always use small sips or bites at a time. Perform 1 or more dry swallows after each bite or sip. After taking a bite of solid foods, chase it down with a sip of liquids. With liquids, hold it in the mouth for 2-3 seconds before attempting to swallow.Be sure to work with a qualified speech language pathologist to further optimize and improve any persistent problems. • Masako Maneuver (0:37)• Mendelsohn Maneuver (1:04)• Supraglottic Swallow (2:24)• Chin Tuck (3:17)• Head Turn Swallow (3:56)• General Tips (4:29)Video created by Dr. Christopher Chang:https://www.FauquierENT.netActress:Janine Collinshttps://www.JanineCollins.comStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#swallowtherapy #swallow #swallowing
Medical Jargon Stinks according to #Barbaras Rhabarberbar by Bodo Wartke & Marti Fischer Fauquier ENT 2024-05-27 | Just for fun!Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#barbara #germanrap
Optokinetic Stripes (Left to Right) for Head Roll Exercises to Treat Mal de Debarquement Syndrome Fauquier ENT 2024-05-23 | Moving red stripes from left to right used in the treatment of Mal de Debarquement Syndrome (MdDS) with metronome at 10 bpm. Known as optokinetic head roll exercises, the moving stripes are utilized to help resolve symptoms in up to 70% of patients who suffer from this condition within 5 days.Video on How to Perform Head Roll Exercise: youtu.be/a4402WcaQA4The video is exactly 5 minutes long which is the recommended duration to perform these exercises up to 8 times a day. Also played is a metronome at 10 bpm which is the recommended duration of one head roll cycle. Finally, do play this on as large a screen as possible and make sure the optokinetic stripes fill at least 80% of your vision!To optimize clarity, the video was made at 4K resolution at 60fps.Full playlist of red/black thin/thick stripes moving either right/left:youtube.com/playlist?list=PLblLJazSSA3R1UjH-rLu6kYTPGh5Vfb-rHead Roll ExerciseFirst, figure out the dominant direction of your rocking or swaying. Now this can be a little tricky because the rocking or swaying is moving back and forth… But, most people can identify a dominant side to their swaying or rocking. So even though you're going back and forth a lot of times, you'll feel more of a pull in one direction versus the other. See if you can identify what that direction is. If you can’t, you're going to just pick one side and go with that one. If after a few days, there is no improvement, then you can switch sides. Once you have picked a side, you will set the optokinetic stimulation stripes to go in the opposite direction. SO for example, if your sway is right side dominant, you will set the optokinetic stripes to move in the left direction. Once you have picked a direction, hold the screen in front of the eyes such that it fills at least 80% of your visual field.You do not want it too far from your eyes, but close enough that it really fills up most your vision.There is a metronome audio in this video set to 10 beats per minute. Each beat is going to represent one full cycle of head movement.Without turning the head, you will first bring one ear down towards the same side shoulder. Then move the head back to neutral position. Then move the opposite ear towards the opposite shoulder, then back to neutral position. This completes one cycle.Try to make the head movement as one continuous smooth motion without stopping at any point.Each session should be performed for 3-5 minutes. Make sure to observe your physical reactions to the exercise and if you start to feel really ill, then stop and take some grounding breaths and try again later.In order to be truly helpful, this exercise needs to be performed up to 8 times a day.If this exercise helps, you should start to feel improvement within 5 days. If you don't have an improvement in the first five days, then either this exercise will not work for you OR you picked the wrong side to begin with in which case, you would repeat this entire exercise again, but in the opposite direction.Reference:Readaptation of the vestibulo-ocular reflex relieves the mal de debarquement syndrome. Neurol. 2014 Jul 15:5:124. pubmed.ncbi.nlm.nih.gov/25076935Sham-Controlled Study of Optokinetic Stimuli as Treatment for Mal de Debarquement Syndrome. Front Neurol. 2018 Oct 25:9:887. pubmed.ncbi.nlm.nih.gov/30410464Optokinetic motion sickness and pseudo-Coriolis effects induced by moving visual stimuli. Acta Otolaryngol 76(5): 339-348. 1973. pubmed.ncbi.nlm.nih.gov/4543918Prevention of overt motion sickness by incremental exposure to otherwise highly stressful coriolis accelerations. Aerospace Medicine 40(2): 142-148. 1969. pubmed.ncbi.nlm.nih.gov/5304382Mal de debarquement. Arch Otolaryngol Head Neck Surg 125(6): 615-620. 1999. pubmed.ncbi.nlm.nih.gov/10367916Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#mdds #maldedebarquement #chronicdizziness #dizziness
Optokinetic Stripes (Right to Left) for Head Roll Exercises to Treat Mal de Debarquement Syndrome Fauquier ENT 2024-05-23 | Moving red stripes from right to left used in the treatment of Mal de Debarquement Syndrome (MdDS) with metronome at 10 bpm. Known as optokinetic head roll exercises, the moving stripes are utilized to help resolve symptoms in up to 70% of patients who suffer from this condition within 5 days.Video on How to Perform Head Roll Exercise: youtu.be/a4402WcaQA4The video is exactly 5 minutes long which is the recommended duration to perform these exercises up to 8 times a day. Also played is a metronome at 10 bpm which is the recommended duration of one head roll cycle. Finally, do play this on as large a screen as possible and make sure the optokinetic stripes fill at least 80% of your vision!To optimize clarity, the video was made at 4K resolution at 60fps.Full playlist of red/black thin/thick stripes moving either right/left:youtube.com/playlist?list=PLblLJazSSA3R1UjH-rLu6kYTPGh5Vfb-rHead Roll ExerciseFirst, figure out the dominant direction of your rocking or swaying. Now this can be a little tricky because the rocking or swaying is moving back and forth… But, most people can identify a dominant side to their swaying or rocking. So even though you're going back and forth a lot of times, you'll feel more of a pull in one direction versus the other. See if you can identify what that direction is. If you can’t, you're going to just pick one side and go with that one. If after a few days, there is no improvement, then you can switch sides. Once you have picked a side, you will set the optokinetic stimulation stripes to go in the opposite direction. SO for example, if your sway is right side dominant, you will set the optokinetic stripes to move in the left direction. Once you have picked a direction, hold the screen in front of the eyes such that it fills at least 80% of your visual field.You do not want it too far from your eyes, but close enough that it really fills up most your vision.There is a metronome audio in this video set to 10 beats per minute. Each beat is going to represent one full cycle of head movement.Without turning the head, you will first bring one ear down towards the same side shoulder. Then move the head back to neutral position. Then move the opposite ear towards the opposite shoulder, then back to neutral position. This completes one cycle.Try to make the head movement as one continuous smooth motion without stopping at any point.Each session should be performed for 3-5 minutes. Make sure to observe your physical reactions to the exercise and if you start to feel really ill, then stop and take some grounding breaths and try again later.In order to be truly helpful, this exercise needs to be performed up to 8 times a day.If this exercise helps, you should start to feel improvement within 5 days. If you don't have an improvement in the first five days, then either this exercise will not work for you OR you picked the wrong side to begin with in which case, you would repeat this entire exercise again, but in the opposite direction.Reference:Readaptation of the vestibulo-ocular reflex relieves the mal de debarquement syndrome. Neurol. 2014 Jul 15:5:124. pubmed.ncbi.nlm.nih.gov/25076935Sham-Controlled Study of Optokinetic Stimuli as Treatment for Mal de Debarquement Syndrome. Front Neurol. 2018 Oct 25:9:887. pubmed.ncbi.nlm.nih.gov/30410464Optokinetic motion sickness and pseudo-Coriolis effects induced by moving visual stimuli. Acta Otolaryngol 76(5): 339-348. 1973. pubmed.ncbi.nlm.nih.gov/4543918Prevention of overt motion sickness by incremental exposure to otherwise highly stressful coriolis accelerations. Aerospace Medicine 40(2): 142-148. 1969. pubmed.ncbi.nlm.nih.gov/5304382Mal de debarquement. Arch Otolaryngol Head Neck Surg 125(6): 615-620. 1999. pubmed.ncbi.nlm.nih.gov/10367916Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#mdds #maldedebarquement #chronicdizziness #dizziness
Optokinetic Stripes (Left to Right) for Head Roll Exercises to Treat Mal de Debarquement Syndrome Fauquier ENT 2024-05-22 | Moving black stripes from left to right used in the treatment of Mal de Debarquement Syndrome (MdDS) with metronome at 10 bpm. Known as optokinetic head roll exercises, the moving stripes are utilized to help resolve symptoms in up to 70% of patients who suffer from this condition within 5 days.Video on How to Perform Head Roll Exercise: youtu.be/a4402WcaQA4The video is exactly 5 minutes long which is the recommended duration to perform these exercises up to 8 times a day. Also played is a metronome at 10 bpm which is the recommended duration of one head roll cycle. Finally, do play this on as large a screen as possible and make sure the optokinetic stripes fill at least 80% of your vision!To optimize clarity, the video was made at 4K resolution at 60fps.Full playlist of red/black thin/thick stripes moving either right/left:youtube.com/playlist?list=PLblLJazSSA3R1UjH-rLu6kYTPGh5Vfb-rHead Roll ExerciseFirst, figure out the dominant direction of your rocking or swaying. Now this can be a little tricky because the rocking or swaying is moving back and forth… But, most people can identify a dominant side to their swaying or rocking. So even though you're going back and forth a lot of times, you'll feel more of a pull in one direction versus the other. See if you can identify what that direction is. If you can’t, you're going to just pick one side and go with that one. If after a few days, there is no improvement, then you can switch sides. Once you have picked a side, you will set the optokinetic stimulation stripes to go in the opposite direction. SO for example, if your sway is right side dominant, you will set the optokinetic stripes to move in the left direction. Once you have picked a direction, hold the screen in front of the eyes such that it fills at least 80% of your visual field.You do not want it too far from your eyes, but close enough that it really fills up most your vision.There is a metronome audio in this video set to 10 beats per minute. Each beat is going to represent one full cycle of head movement.Without turning the head, you will first bring one ear down towards the same side shoulder. Then move the head back to neutral position. Then move the opposite ear towards the opposite shoulder, then back to neutral position. This completes one cycle.Try to make the head movement as one continuous smooth motion without stopping at any point.Each session should be performed for 3-5 minutes. Make sure to observe your physical reactions to the exercise and if you start to feel really ill, then stop and take some grounding breaths and try again later.In order to be truly helpful, this exercise needs to be performed up to 8 times a day.If this exercise helps, you should start to feel improvement within 5 days. If you don't have an improvement in the first five days, then either this exercise will not work for you OR you picked the wrong side to begin with in which case, you would repeat this entire exercise again, but in the opposite direction.Reference:Readaptation of the vestibulo-ocular reflex relieves the mal de debarquement syndrome. Neurol. 2014 Jul 15:5:124. pubmed.ncbi.nlm.nih.gov/25076935Sham-Controlled Study of Optokinetic Stimuli as Treatment for Mal de Debarquement Syndrome. Front Neurol. 2018 Oct 25:9:887. pubmed.ncbi.nlm.nih.gov/30410464Optokinetic motion sickness and pseudo-Coriolis effects induced by moving visual stimuli. Acta Otolaryngol 76(5): 339-348. 1973. pubmed.ncbi.nlm.nih.gov/4543918Prevention of overt motion sickness by incremental exposure to otherwise highly stressful coriolis accelerations. Aerospace Medicine 40(2): 142-148. 1969. pubmed.ncbi.nlm.nih.gov/5304382Mal de debarquement. Arch Otolaryngol Head Neck Surg 125(6): 615-620. 1999. pubmed.ncbi.nlm.nih.gov/10367916Video created by Dr. Christopher Chang:https://www.FauquierENT.netStill haven’t subscribed to Fauquier ENT on YouTube? ►► bit.ly/35SazwA#mdds #maldedebarquement #chronicdizziness #dizziness