Uploaded February 2018 | Updated September 2026, 20 hours ago
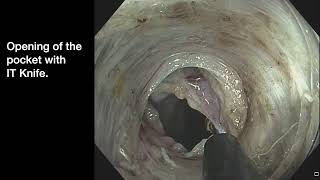
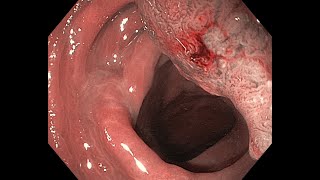
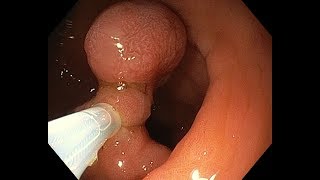
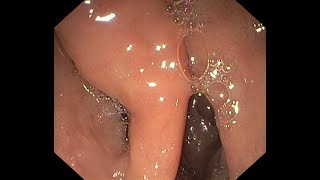
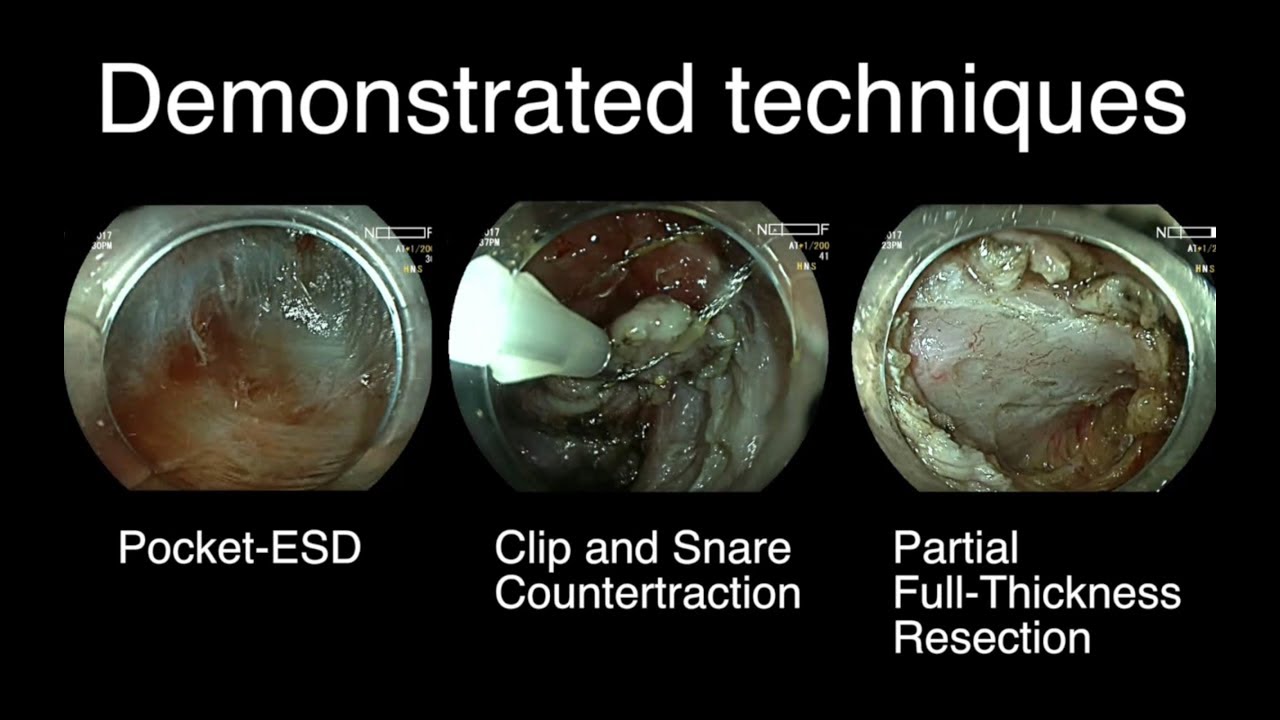
A 68-year-old female patient with history of surgery and radiotherapy for rectal cancer, was referred for endoscopic submucosal dissection (ESD) of a 2 cm in size flat non-granular polyp (Paris IIa+IIc) located in a sub-stenotic segment of the sigmoid colon. The lesion was lifted with a mixture of hyaluronic acid with indigocarmine and hydroxyethyl starch. A small incision was made at the anal side with a needle-type knife (DualKnife 1.5 mm, Olympus, Japan), and the endoscope ((EG-760Z, Fujifilm, Japan) was gently pushed in the submucosal space. A submucosal pocket was created following the external markers, using Endocut Q, Effect 2 for dissection (VIO 3, ERBE, Germany), Forced Coag 25 W for coagulation of small vessels with the tip of the knife and Soft Coag 80W for coagulation of bigger vessels with a Coagrasper (Olympus). Dissection of the right side of the lesion was challenging due to thick fibrosis. A snare was loaded over the extremity of the scope, a clip was placed at the edge of the mucosal flap and then the snare was released and grasped the clip. Back and forward movements of the snare changed the direction of the countertraction as desired. After copious dissection of about 90% of the lesion, the specimen was now hanging from a band of scar tissue fused with the muscle layer. It was hard to recognize the dissection plane; therefore, we proceed to blind dissection taking into account the risk of perforation with a blunt tip knife (ITKnife2, Olympus, Japan). Finally, en-bloc resection was achieved, leaving a circumferential mucosal defect. A 2-cm long transmural defect was recognized leading into a small blind cavity that was completely closed with clips (LifePartners Europe, France). The next day the patient developed diffuse abdominal pain and we proceeded to laparoscopy that showed generalized peritonitis. The site of perforation was firmly closed with the endoscopic clips. The abdomen was washed and one surgical drain was placed. The patient was discharged home on day 2 and had an uneventful recovery. Histology showed R0 resection of a tubulo-villous adenoma with high grade dysplasia. The muscular layer was identified in a small portion of the specimen, corresponding to the area with severe fibrosis. At 7 months of follow-up, the patient remains asymptomatic without signs of recurrence.
A 68-year-old female patient with history of surgery and radiotherapy for rectal cancer, was referred for endoscopic submucosal dissection (ESD) of a 2 cm in size flat non-granular polyp (Paris IIa+IIc) located in a sub-stenotic segment of the sigmoid colon. The lesion was lifted with a mixture of hyaluronic acid with indigocarmine and hydroxyethyl starch. A small incision was made at the anal side with a needle-type knife (DualKnife 1.5 mm, Olympus, Japan), and the endoscope ((EG-760Z, Fujifilm, Japan) was gently pushed in the submucosal space. A submucosal pocket was created following the external markers, using Endocut Q, Effect 2 for dissection (VIO 3, ERBE, Germany), Forced Coag 25 W for coagulation of small vessels with the tip of the knife and Soft Coag 80W for coagulation of bigger vessels with a Coagrasper (Olympus). Dissection of the right side of the lesion was challenging due to thick fibrosis. A snare was loaded over the extremity of the scope, a clip was placed at the edge of the mucosal flap and then the snare was released and grasped the clip. Back and forward movements of the snare changed the direction of the countertraction as desired. After copious dissection of about 90% of the lesion, the specimen was now hanging from a band of scar tissue fused with the muscle layer. It was hard to recognize the dissection plane; therefore, we proceed to blind dissection taking into account the risk of perforation with a blunt tip knife (ITKnife2, Olympus, Japan). Finally, en-bloc resection was achieved, leaving a circumferential mucosal defect. A 2-cm long transmural defect was recognized leading into a small blind cavity that was completely closed with clips (LifePartners Europe, France). The next day the patient developed diffuse abdominal pain and we proceeded to laparoscopy that showed generalized peritonitis. The site of perforation was firmly closed with the endoscopic clips. The abdomen was washed and one surgical drain was placed. The patient was discharged home on day 2 and had an uneventful recovery. Histology showed R0 resection of a tubulo-villous adenoma with high grade dysplasia. The muscular layer was identified in a small portion of the specimen, corresponding to the area with severe fibrosis. At 7 months of follow-up, the patient remains asymptomatic without signs of recurrence.