Uploaded March 2024 | Updated September 2026, 13 hours ago
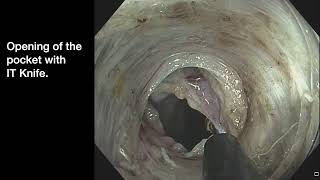
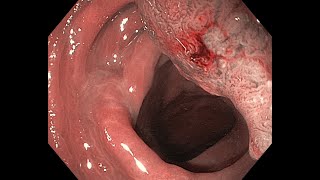
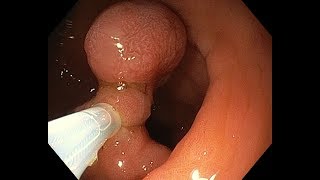
Endoscopic resection of gastrointestinal stromal tumors of the fundus is challenging due to the need for full-thickness resection and the difficulties for defect closure. Submucosal tunneling in direct view through the esophagus can be applied for esophageal tumors and gastric tumors of the cardia near the gastroesophageal junction. However, for tumors located at the fundus it is not feasible. In this video, we present the resection strategy of a gastric gastrointestinal stromal tumor (GIST) located at the fundus with the application of submucosal tunneling endoscopic resection (STER) in retroflexion, combined with clip and band traction, and clip and loop closure of the mucosal entrance. Initially, a horizontal incision was made 2 cms distally to the lesion in retroflexion with Flush Knife BTs 1.5 (Fujifilm, Tokyo, Japan). Then, a short pocket was created. In order to keep the mucosa away from the dissection field, a clip and band complex was applied as previously described. Cautious enucleation of the tumor was continued in retroflexion. Myotomy and detachment of the tumor from the muscle layer was performed with a Hook Knife (Olympus, Tokyo, Japan). Presence of adipose tissue was visible at the end of the resection. After retrieval of the lesion an endoloop was advanced over the scope and was fixed in an open position with clips over the edges of the mucosal defect. Closure of the loop resulted into tight sealing of the mucosal entrance. Next day a CT scan with oral contrast confirmed the absence of leakage. The patient was discharged 48h after the operation and followed a liquid diet for 7 days. Histology showed a GIST with low mitotic index. At one year of follow up the patients has no symptoms or signs of recurrence. In conclusion, we present a novel application of STER for challenging locations where straight tunneling is not feasible.
Published in Endoscopy 2024.
Endoscopic resection of gastrointestinal stromal tumors of the fundus is challenging due to the need for full-thickness resection and the difficulties for defect closure. Submucosal tunneling in direct view through the esophagus can be applied for esophageal tumors and gastric tumors of the cardia near the gastroesophageal junction. However, for tumors located at the fundus it is not feasible. In this video, we present the resection strategy of a gastric gastrointestinal stromal tumor (GIST) located at the fundus with the application of submucosal tunneling endoscopic resection (STER) in retroflexion, combined with clip and band traction, and clip and loop closure of the mucosal entrance. Initially, a horizontal incision was made 2 cms distally to the lesion in retroflexion with Flush Knife BTs 1.5 (Fujifilm, Tokyo, Japan). Then, a short pocket was created. In order to keep the mucosa away from the dissection field, a clip and band complex was applied as previously described. Cautious enucleation of the tumor was continued in retroflexion. Myotomy and detachment of the tumor from the muscle layer was performed with a Hook Knife (Olympus, Tokyo, Japan). Presence of adipose tissue was visible at the end of the resection. After retrieval of the lesion an endoloop was advanced over the scope and was fixed in an open position with clips over the edges of the mucosal defect. Closure of the loop resulted into tight sealing of the mucosal entrance. Next day a CT scan with oral contrast confirmed the absence of leakage. The patient was discharged 48h after the operation and followed a liquid diet for 7 days. Histology showed a GIST with low mitotic index. At one year of follow up the patients has no symptoms or signs of recurrence. In conclusion, we present a novel application of STER for challenging locations where straight tunneling is not feasible.
Published in Endoscopy 2024.