Uploaded November 2019 | Updated September 2026, 1 hour ago
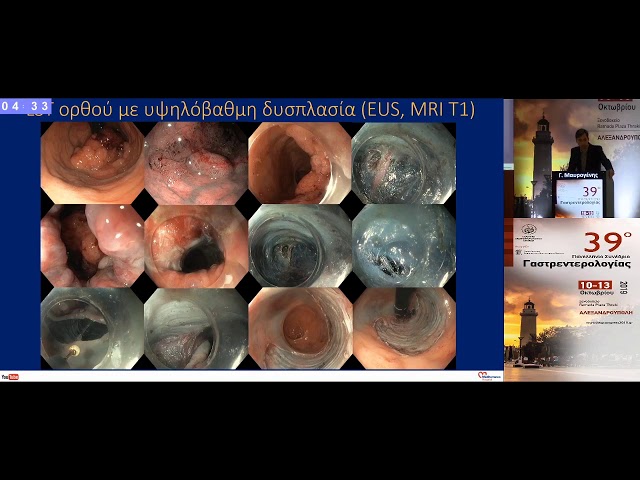
Ποιές είναι οι ενδείξεις για ESD και EMR πολυπόδων παχέος εντέρου; Ομιλία από το Πανελλήνιο συνέδριο γαστρεντερολογίας το 2019 στην Αλεγανδρούπολη. Γεώργιος Μαυρογένης, Γαστρεντερολόγος, Mediterraneo Hospital, Αθήνα.







![Salvage endoscopic wide-field full-thickness resection of T2 rectal cancer without defect closure.
video published in Endoscopy Journal
A 86-year-old male was referred for recurrent bleeding secondary to a 4-cm cT2N0 cancer of the distal rectum (Fig. 1). Tumor staging was negative for metastasis. She had history of severe aortic stenosis and atrial fibrillation under anticoagulants, making her a poor candidate for surgical treatment by total mesorectal excision. After multidisciplinary approach, and informed patient consent, we performed a palliative endoscopic resection of the tumor by means of endoscopic submucosal techniques under propofol sedation (Video 1). After circumferential muscular incision, (Fig. 2, 3) the specimen was progressively dissected from the perirectal fat using a square tip ESD-Knife (Square-Knife, Endoaccess, Garbsen, Germany) in spray coagulation mode (Effect 3.0, VIO3, ERBE, Tübingen, Germany). Large perirectal vessels were coagulated with hot biopsy forceps. No major bleeding was encountered. At the end of the procedure, which lasted 80 minutes, the hemi-circumferential wall-defect was left open (Fig. 4, 5), since this approach has been demonstrated to be safe after surgical local resections [1]. The patient received broad spectrum antibiotics and liquid diet for 1 week. She was hospitalized for 2 days and had an uneventful recovery. One month later, endoscopy confirmed complete wound healing and the patient received local radiotherapy. At 2 years of endoscopic and radiologic follow-up, she remains asymptomatic, without evidence of local recurrence or distal metastasis on imaging and endoscopy. In conclusion, we presented an endoscopic salvage resection of a symptomatic T2 rectal cancer in a patient who was a poor candidate for transabdominal surgery. Local excision is an acceptable treatment for T1N0 early rectal cancer, however there are limited data for high-risk T1 and T2 tumors [2,3]. In a meta-analysis, pT1/pT2 rectal cancers treated with local excision and adjuvant (chemo)radiotherapy were associated with a 14% local recurrence rate and 9% distant recurrence [4]. Although this approach cannot be generalized, we demonstrated the feasibility of endoscopic excision in highly selected cases. Salvage endoscopic wide-field full-thickness resection of T2 rectal cancer without defect closure.](https://i.ytimg.com/vi/gZrzGHdzQlc/mqdefault.jpg)
