Uploaded July 2026 | Updated September 2026, 1 week ago
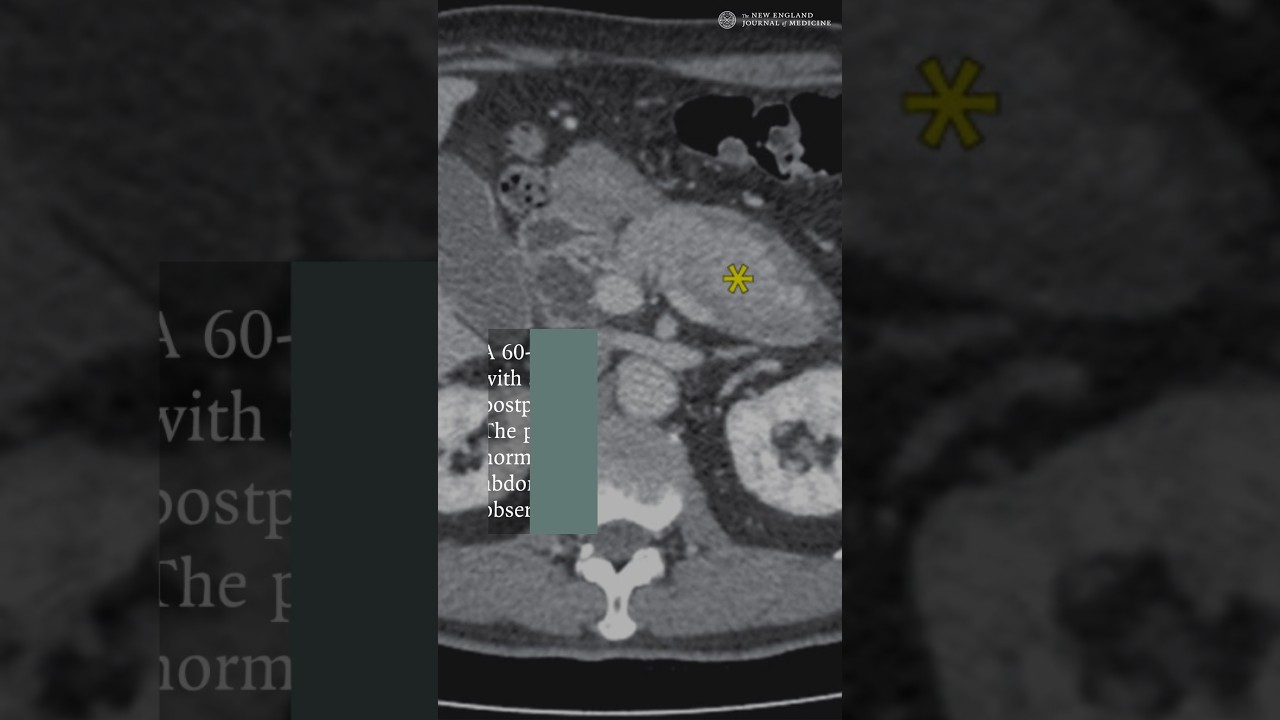
A 60-year-old man presented with a 1-month history of postprandial epigastric pain. The physical examination was normal, with no jaundice or abdominal tenderness observed. Laboratory testing showed mild elevations in levels of alanine aminotransferase, aspartate aminotransferase, and alkaline phosphatase. CT of the abdomen with contrast showed a diffusely enlarged pancreas with a capsule-like rim of low attenuation. The serum IgG4 level was elevated. Endoscopic retrograde cholangiopancreatography identified an intrapancreatic distal bile-duct stricture. Histopathological analysis of a fine-needle aspiration biopsy specimen from the pancreas was limited by crush artifact but showed lymphoplasmacytic infiltration, fibrosis, chronic inflammation, and no cancer. What is the most appropriate next step in management?
Submit your answer at NEJM.org.
#nejm
A 60-year-old man presented with a 1-month history of postprandial epigastric pain. The physical examination was normal, with no jaundice or abdominal tenderness observed. Laboratory testing showed mild elevations in levels of alanine aminotransferase, aspartate aminotransferase, and alkaline phosphatase. CT of the abdomen with contrast showed a diffusely enlarged pancreas with a capsule-like rim of low attenuation. The serum IgG4 level was elevated. Endoscopic retrograde cholangiopancreatography identified an intrapancreatic distal bile-duct stricture. Histopathological analysis of a fine-needle aspiration biopsy specimen from the pancreas was limited by crush artifact but showed lymphoplasmacytic infiltration, fibrosis, chronic inflammation, and no cancer. What is the most appropriate next step in management?
Submit your answer at NEJM.org.
#nejm







